
- EN
- DE

Fungi
Differential Diagnosis of Histoplasma Species:
Pneumocystis jirovecii

- Organ System
- Respiratory Tract
- Diagnostic Method
- Cytology, Histology
- Geographical Region
- Dry Areas,
- Islands,
- Tropical and Subtropical Region,
- Polar and Subpolar Zone,
- Temperate Zone
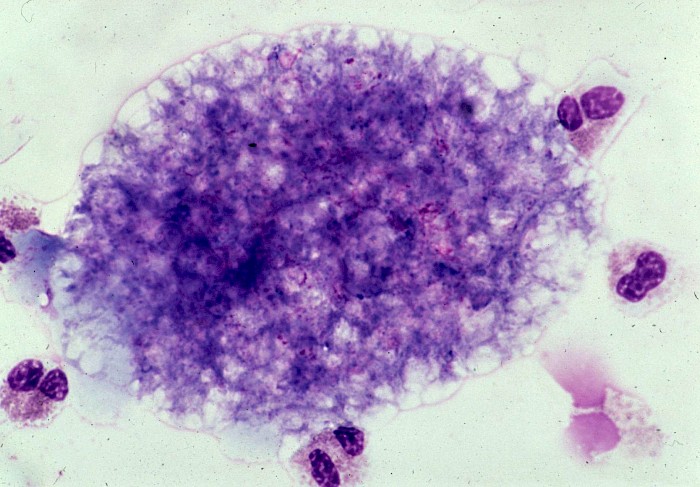
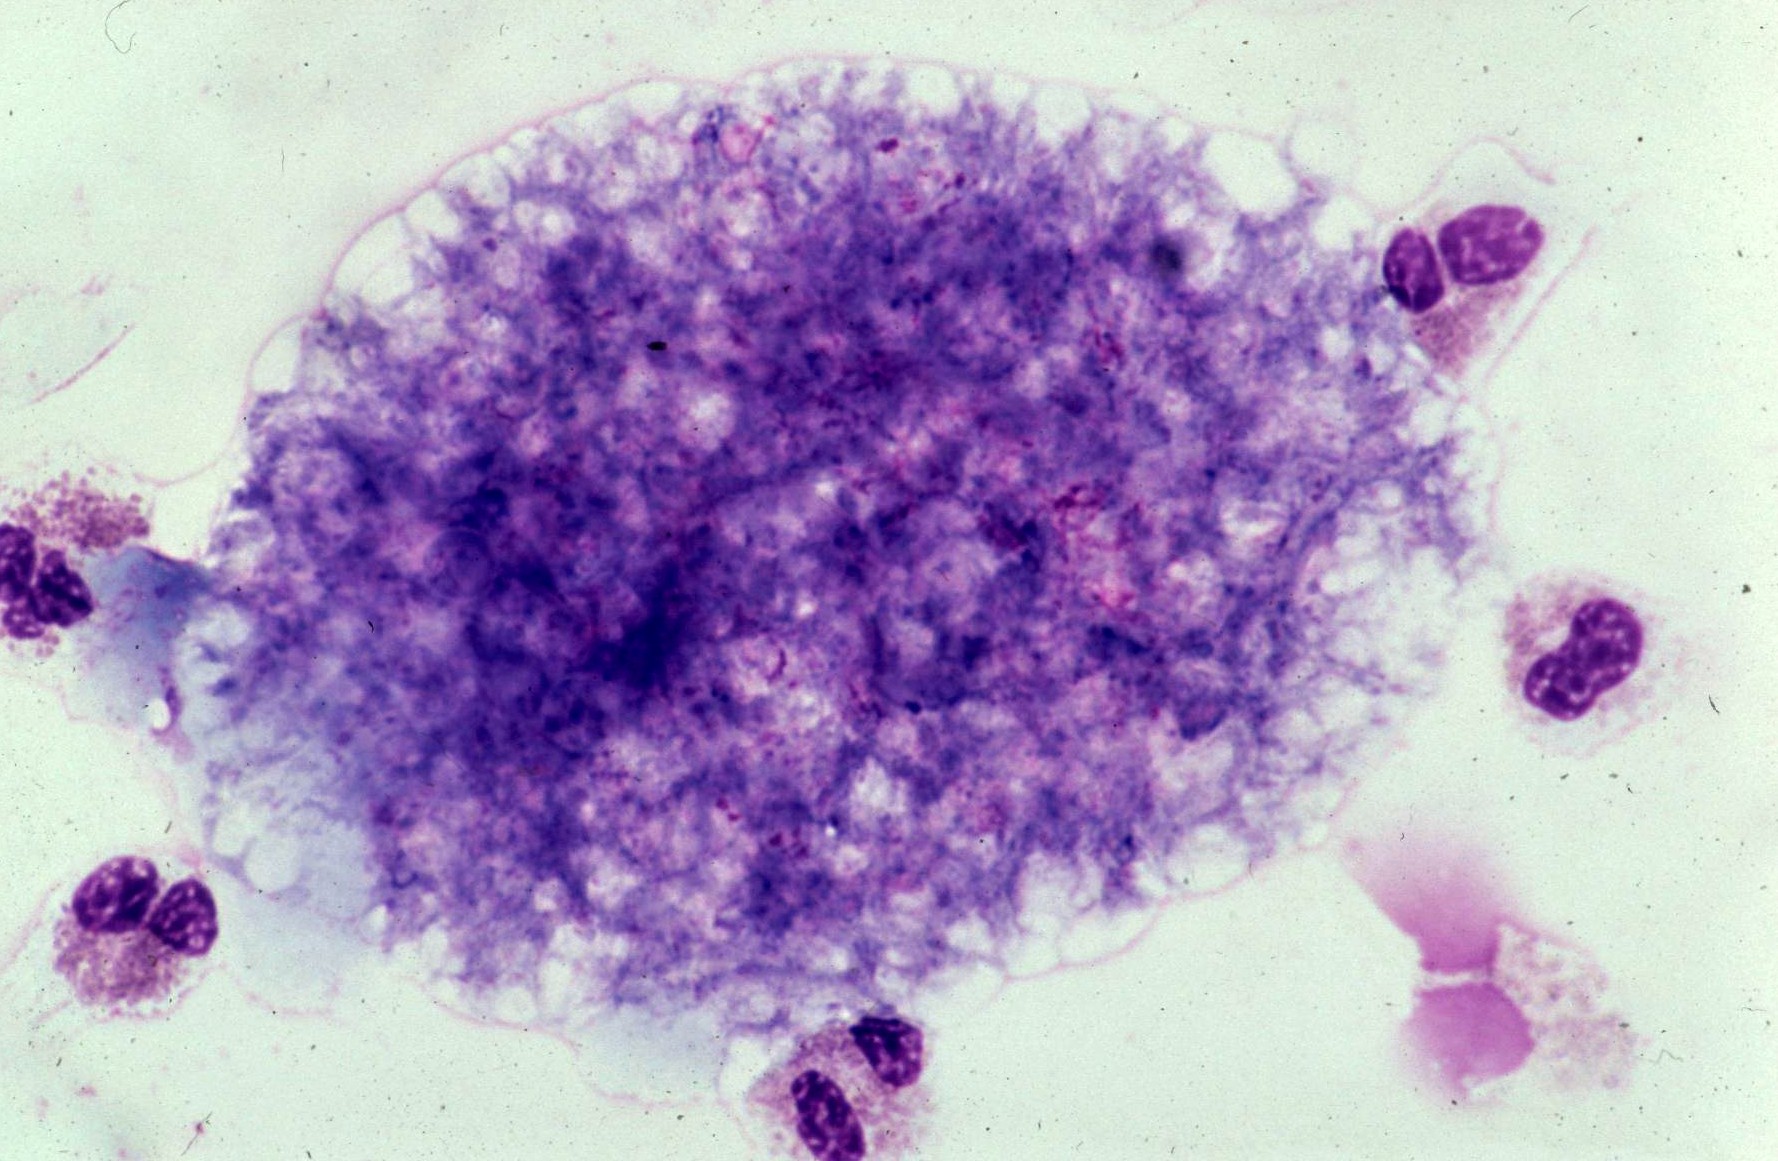 BAL, colonies consisting of numerous round…
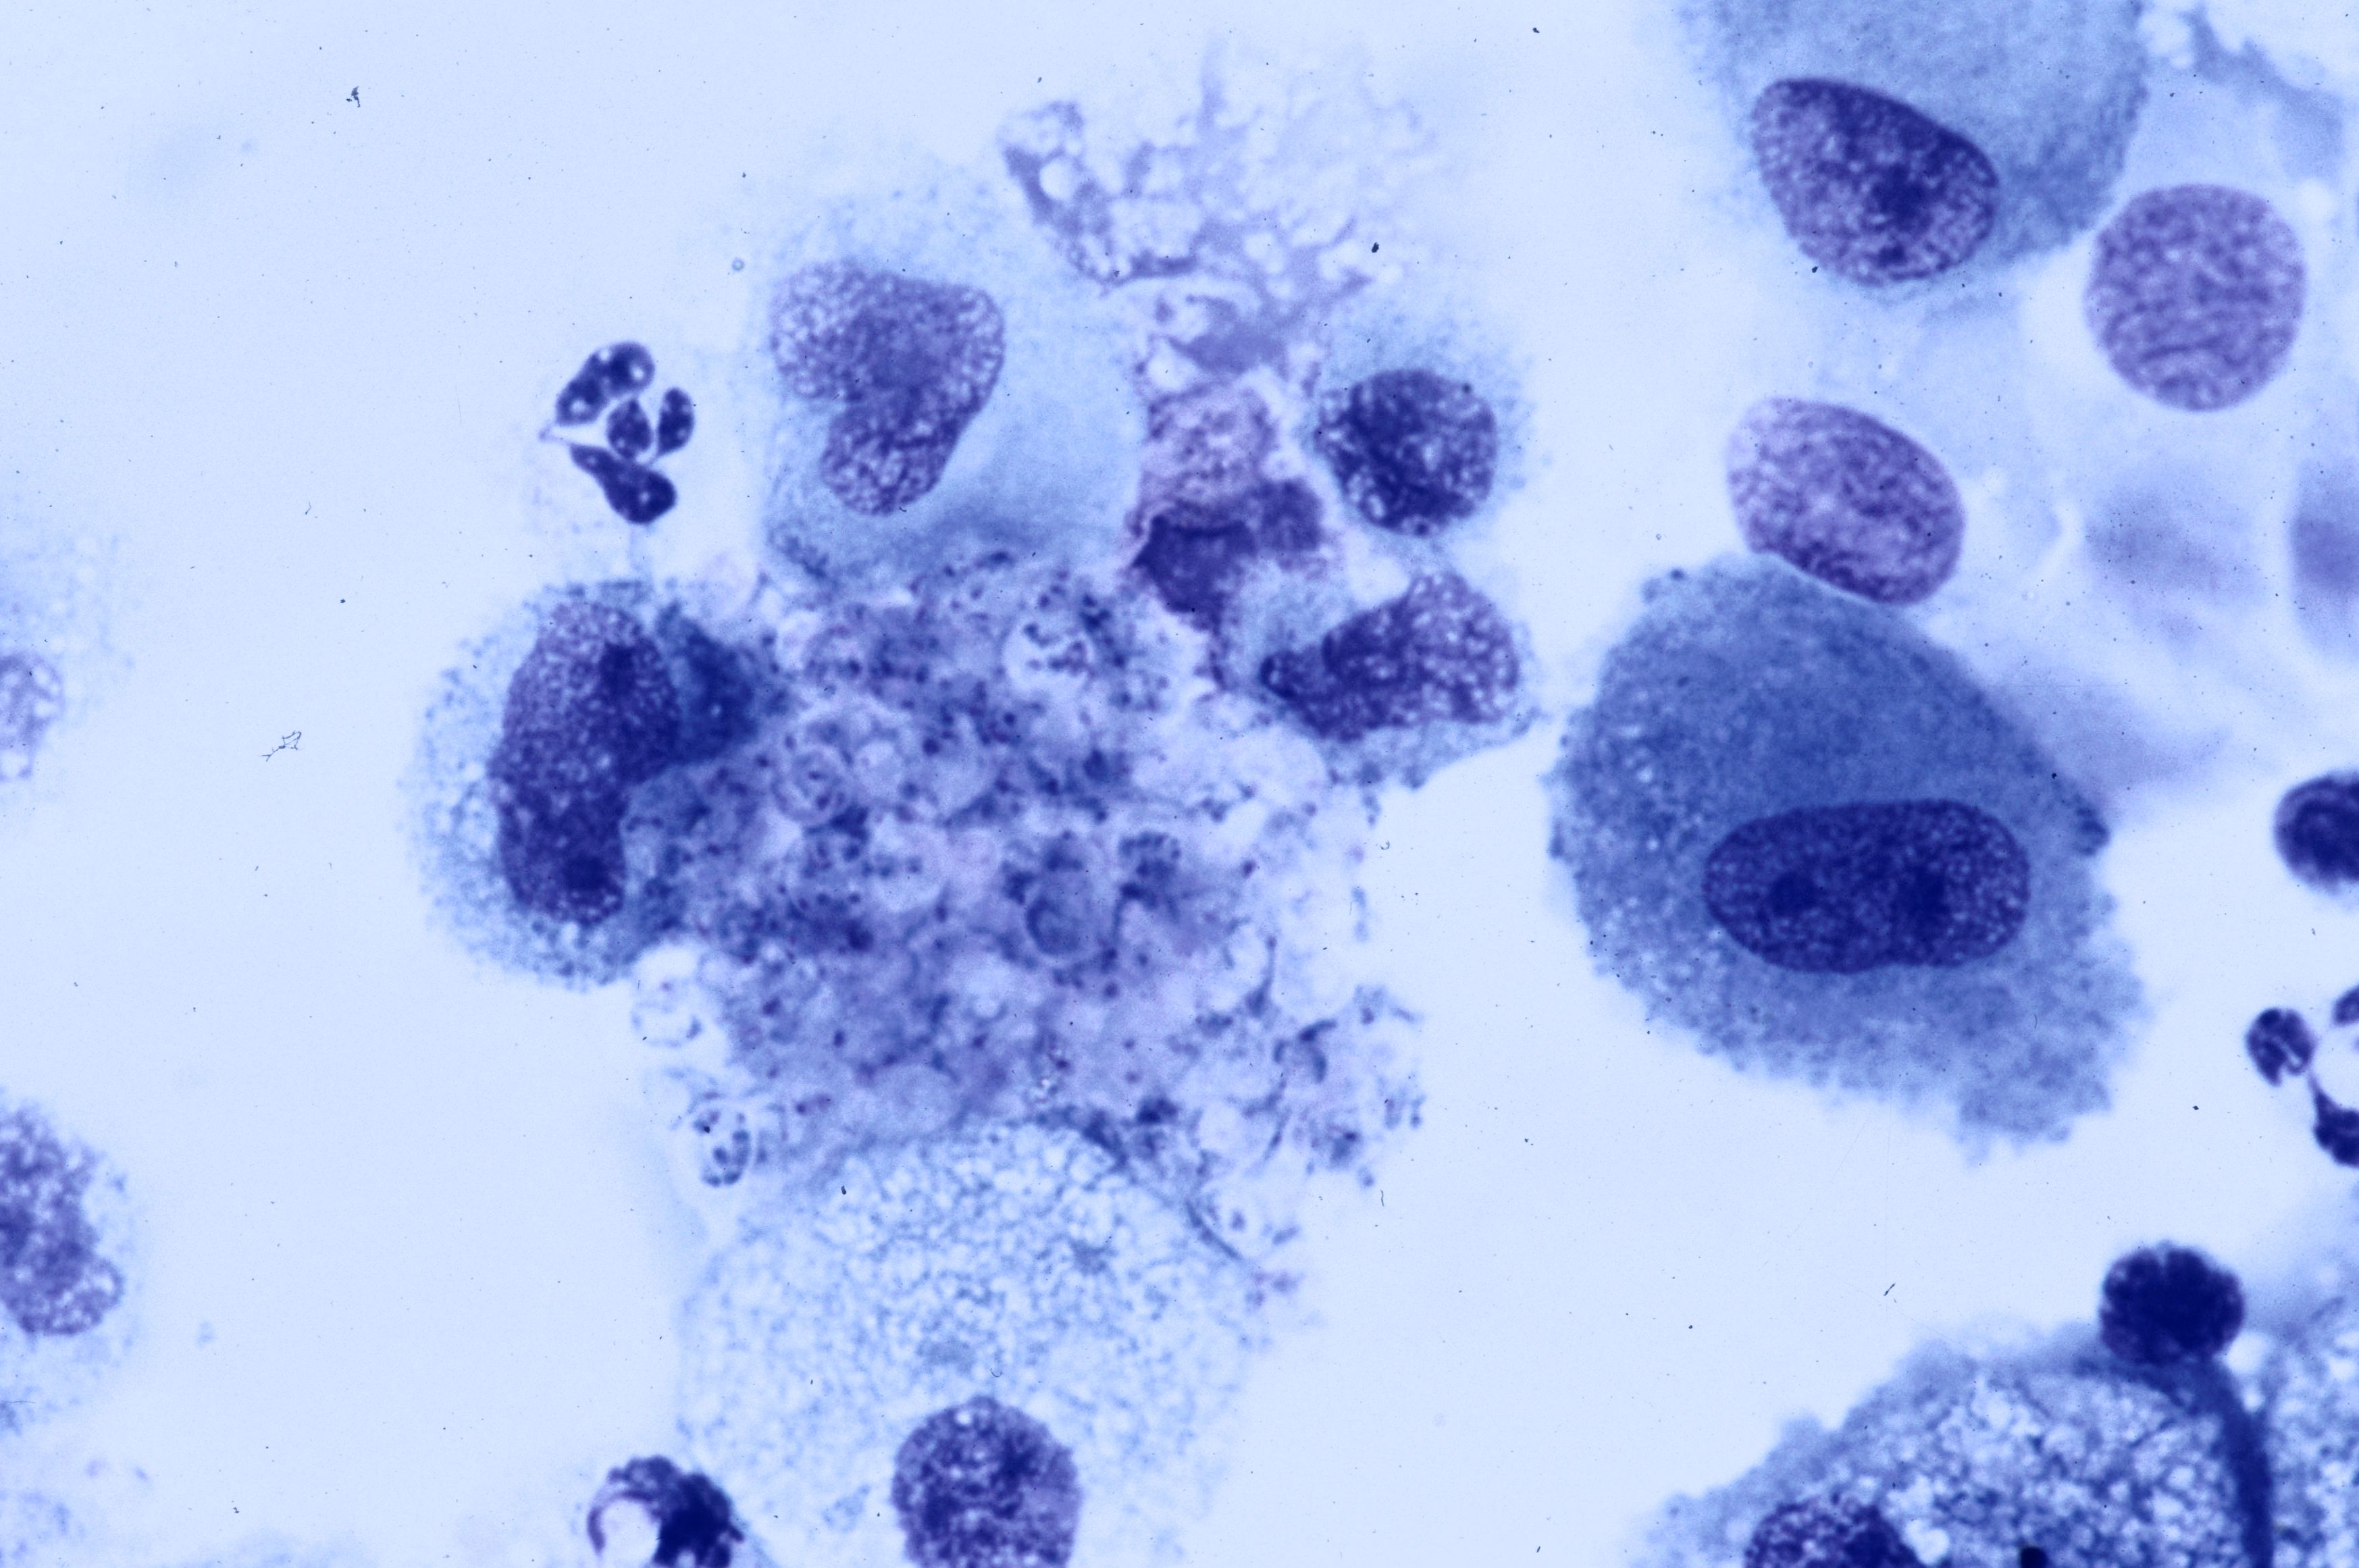 BAL, colonies consisting of numerous round…
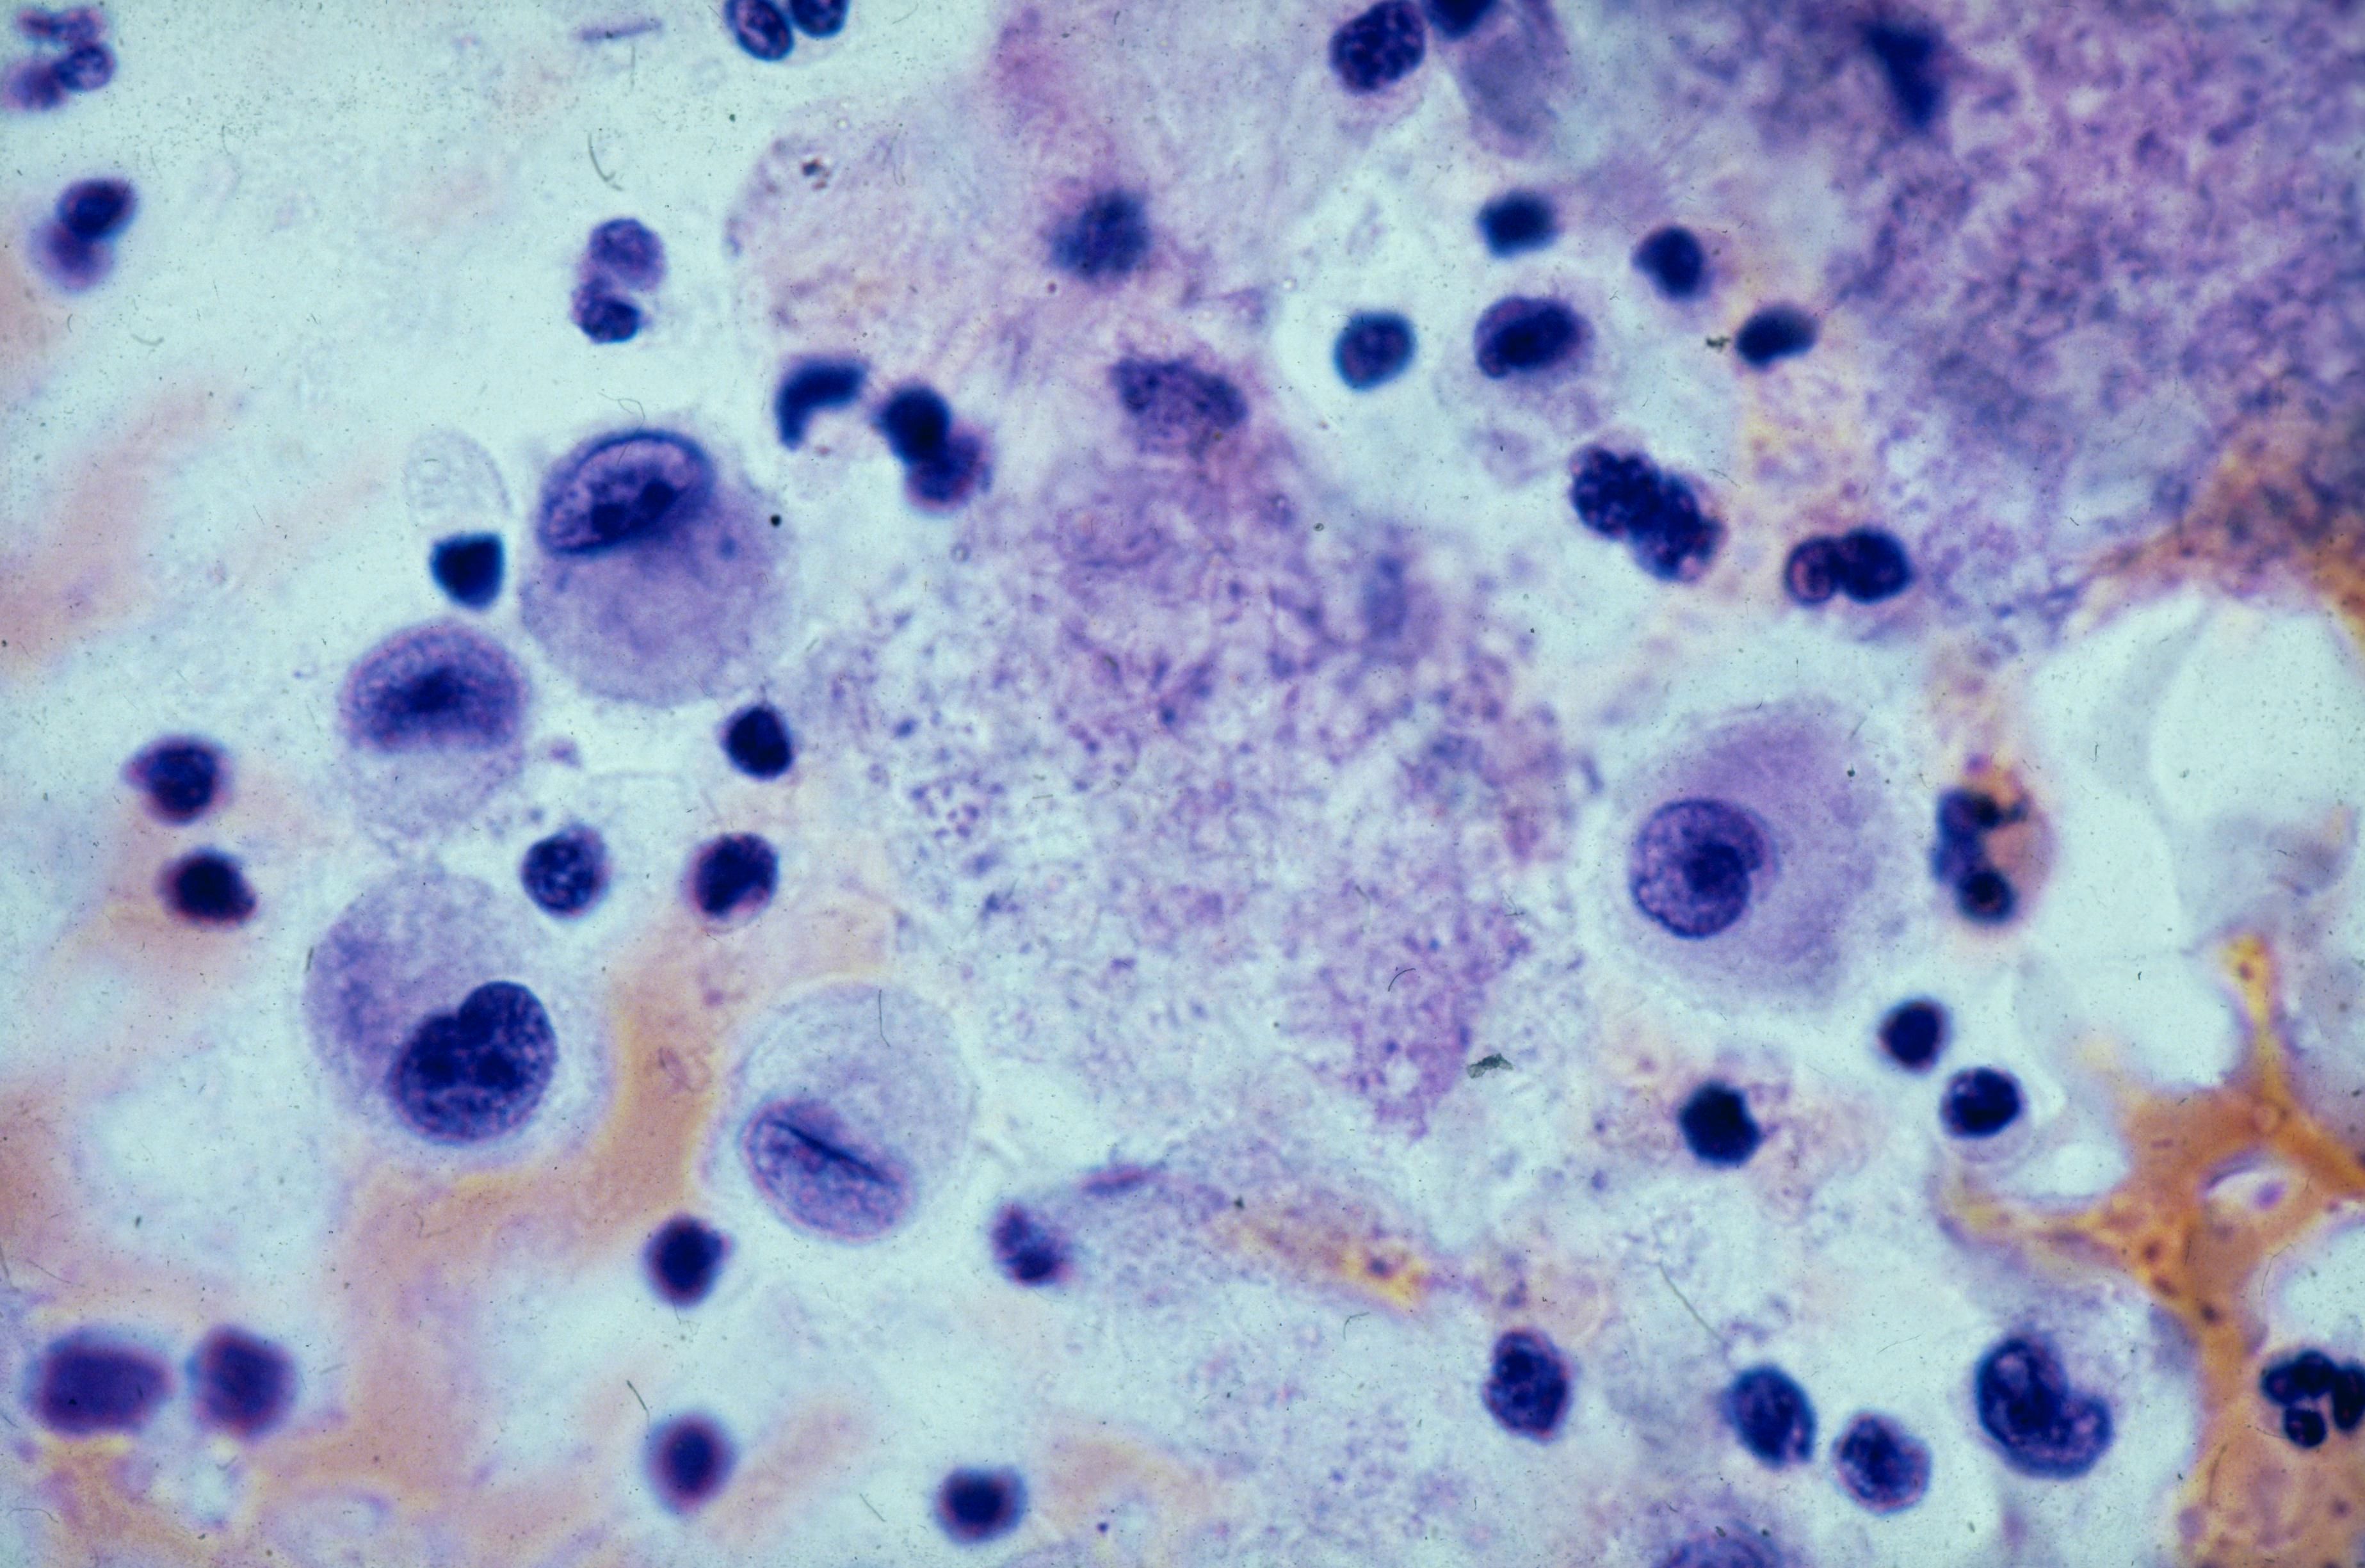 BAL, colonies consisting of dot- or…
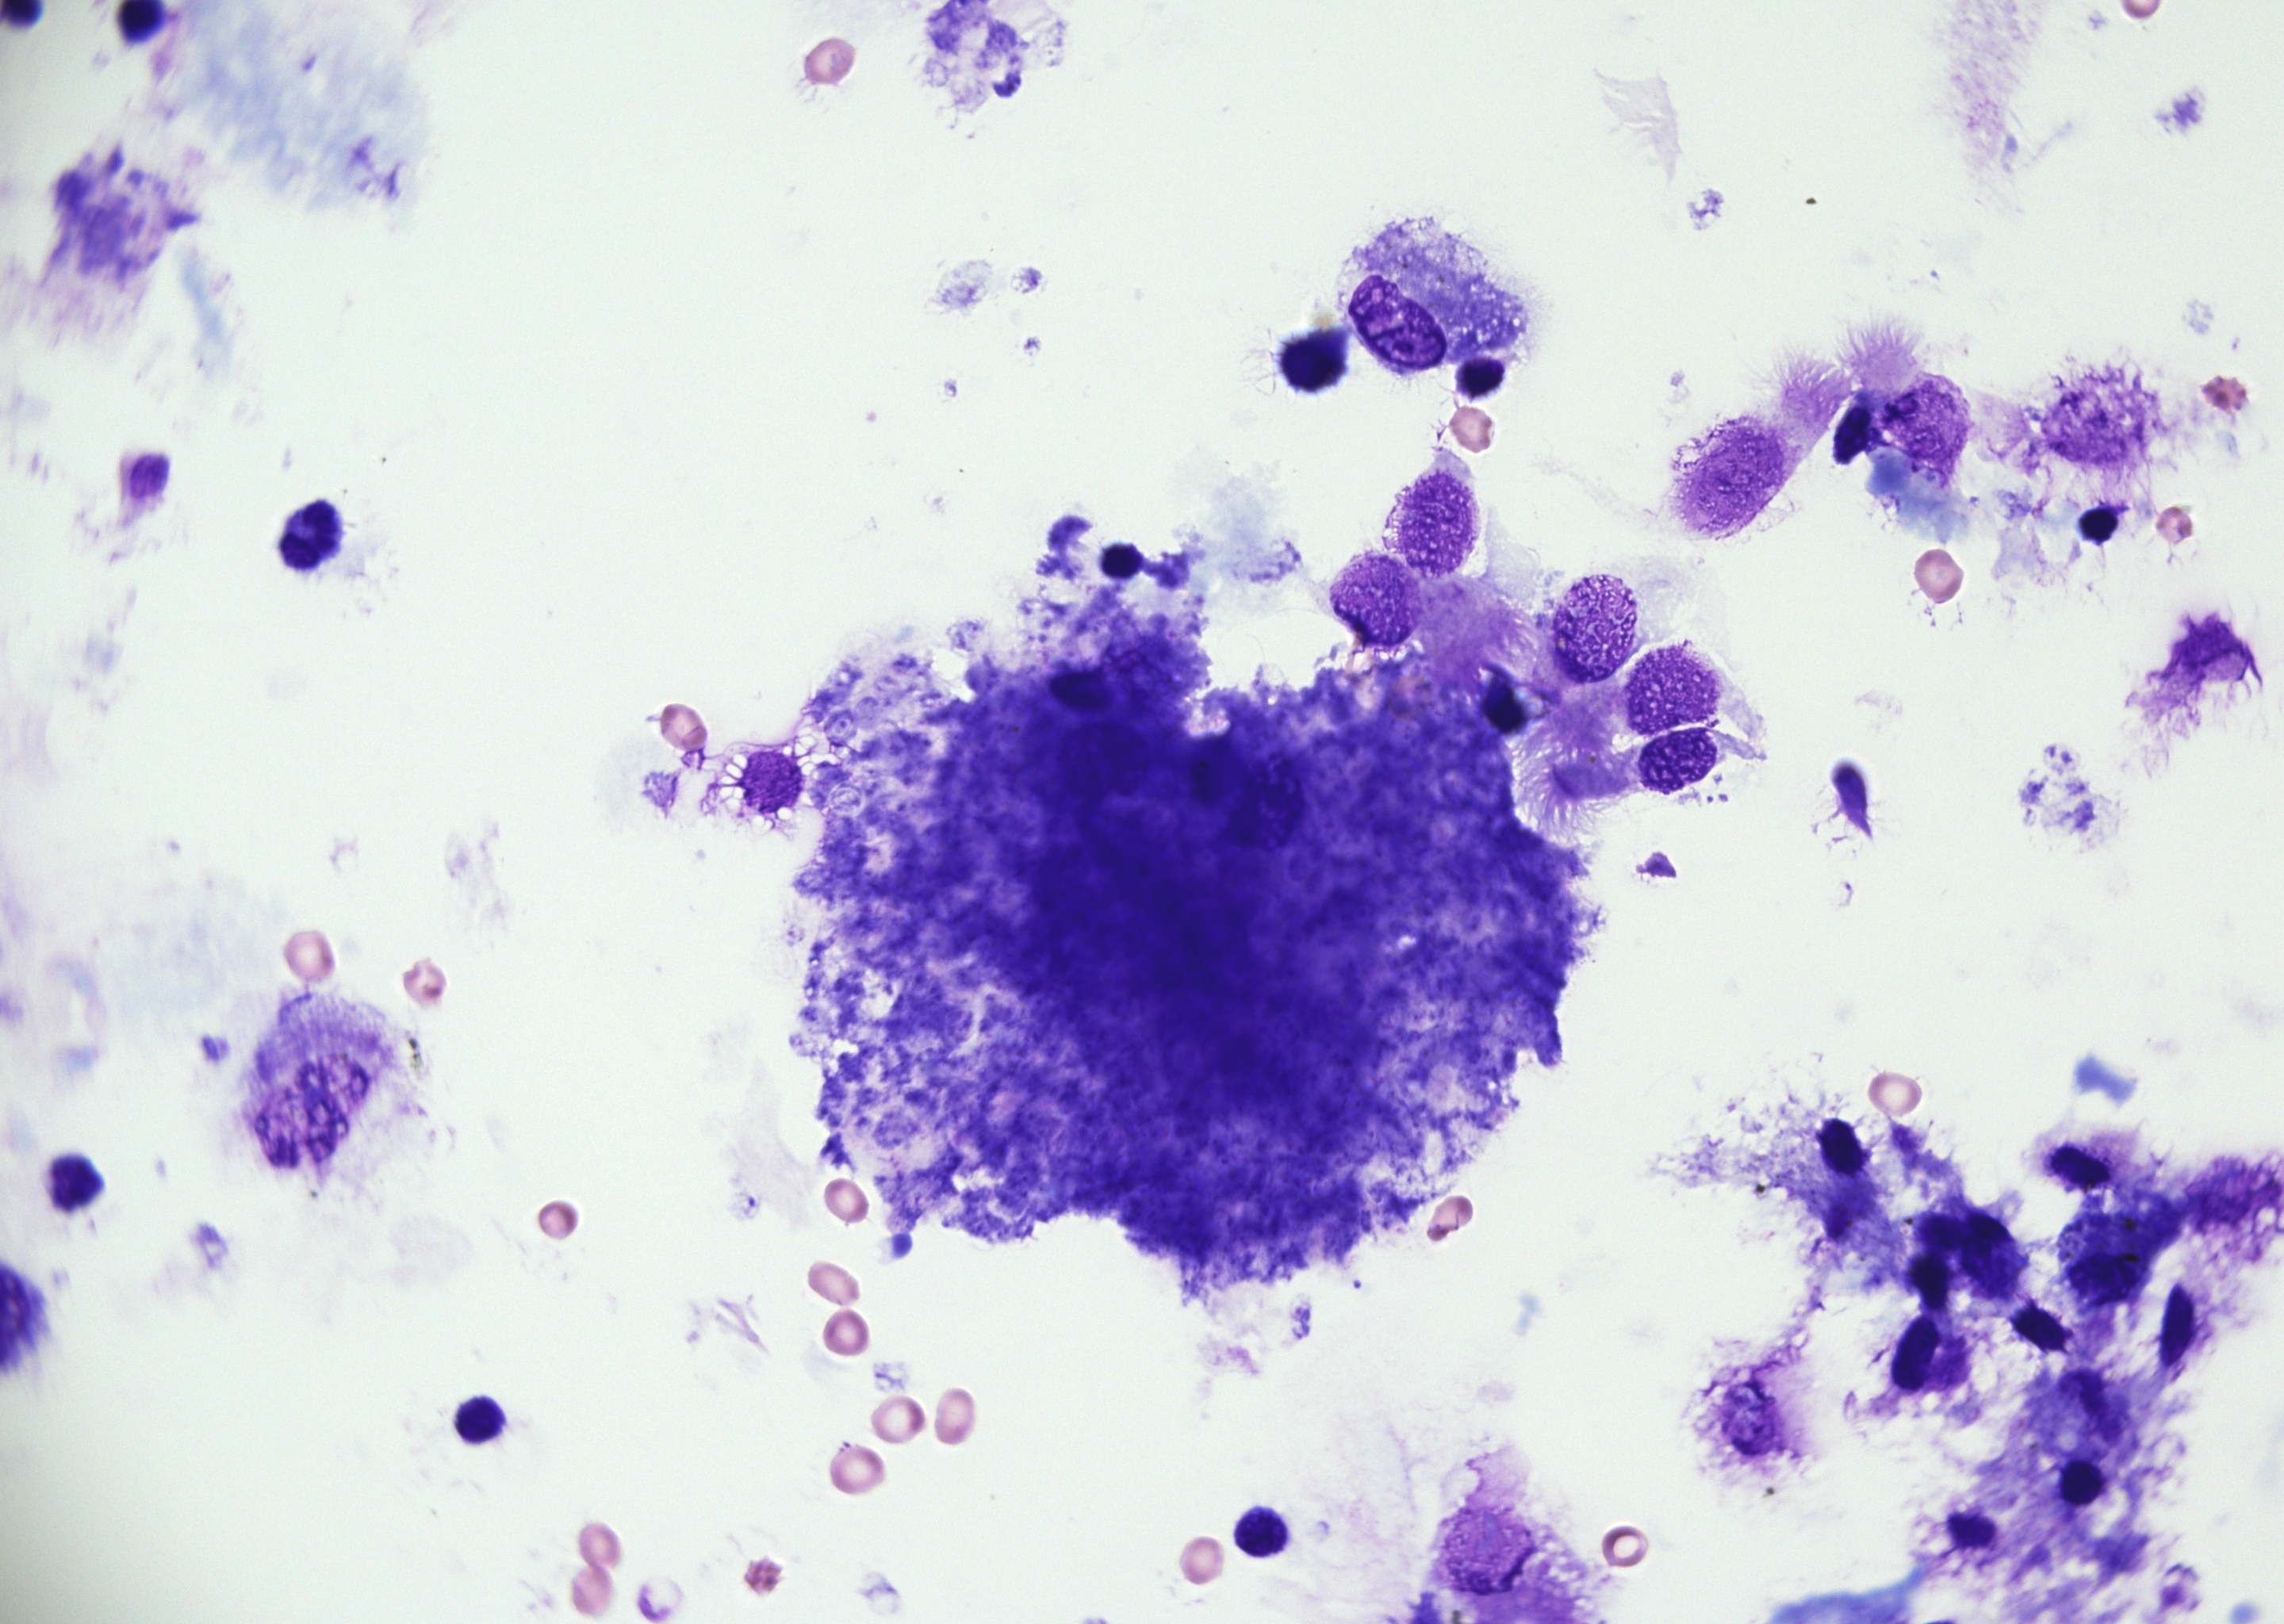 BAL with a colony of numerous round to oval…
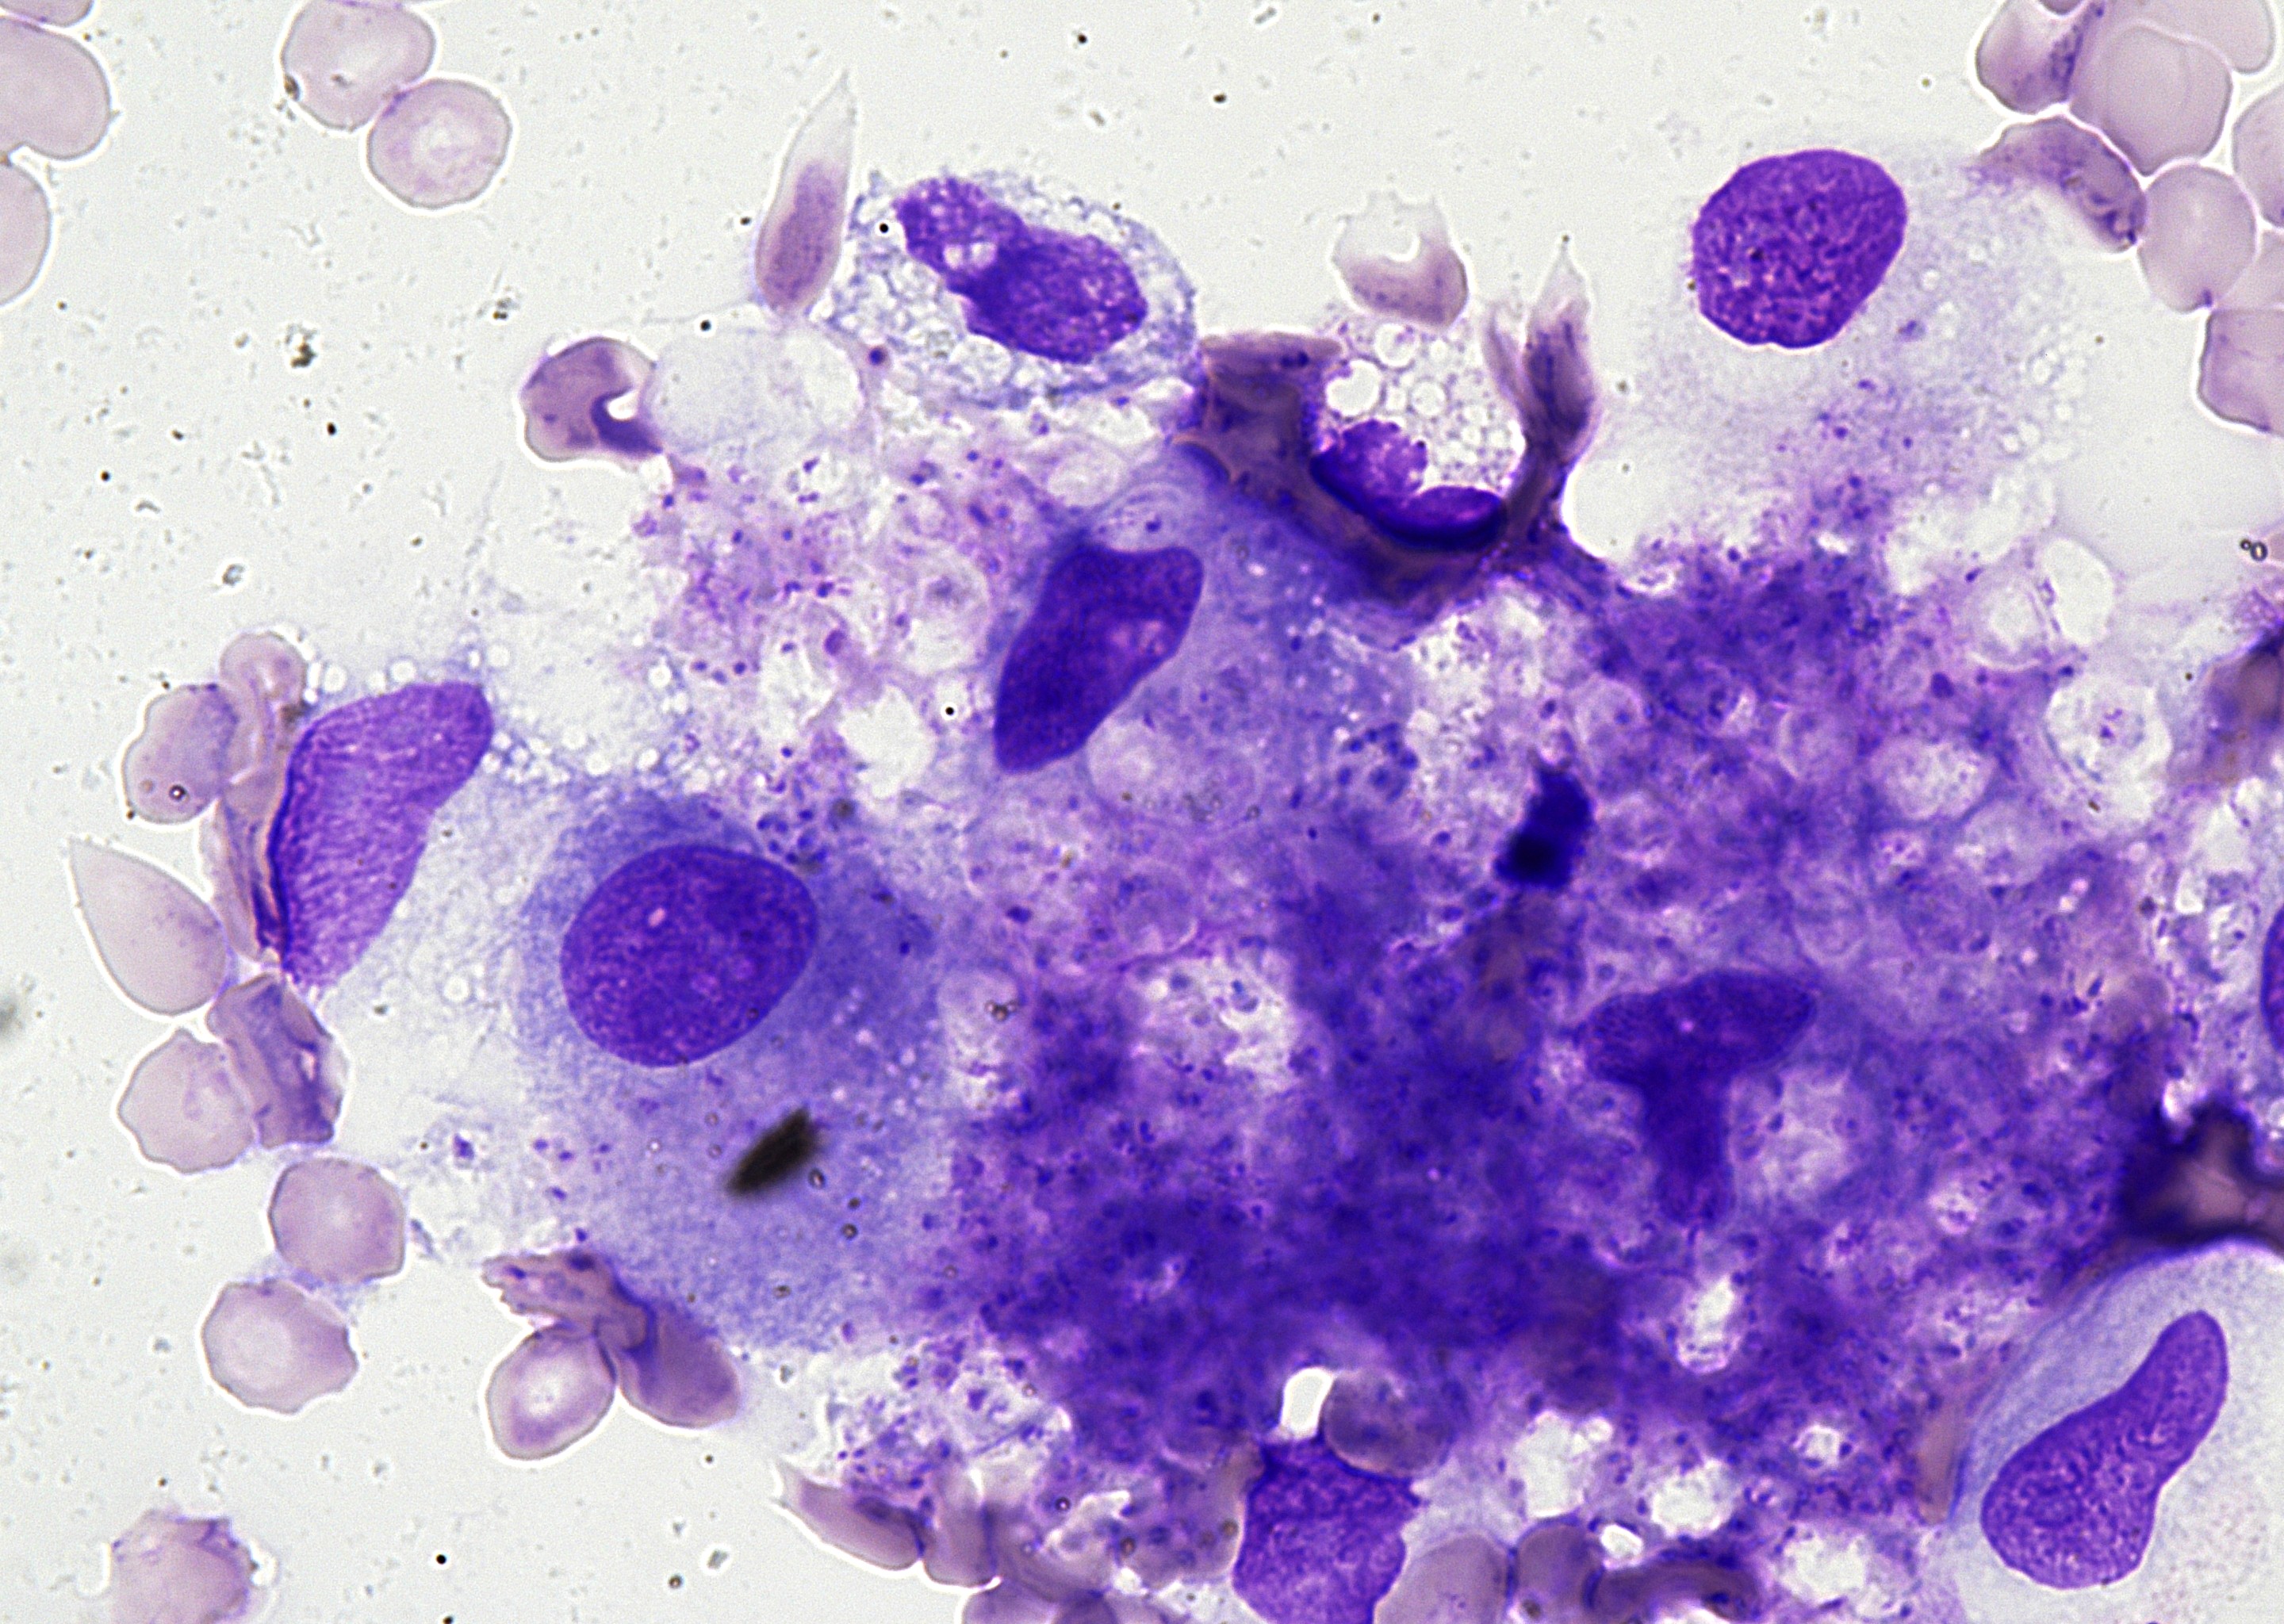 BAL with numerous round to oval cysts with…
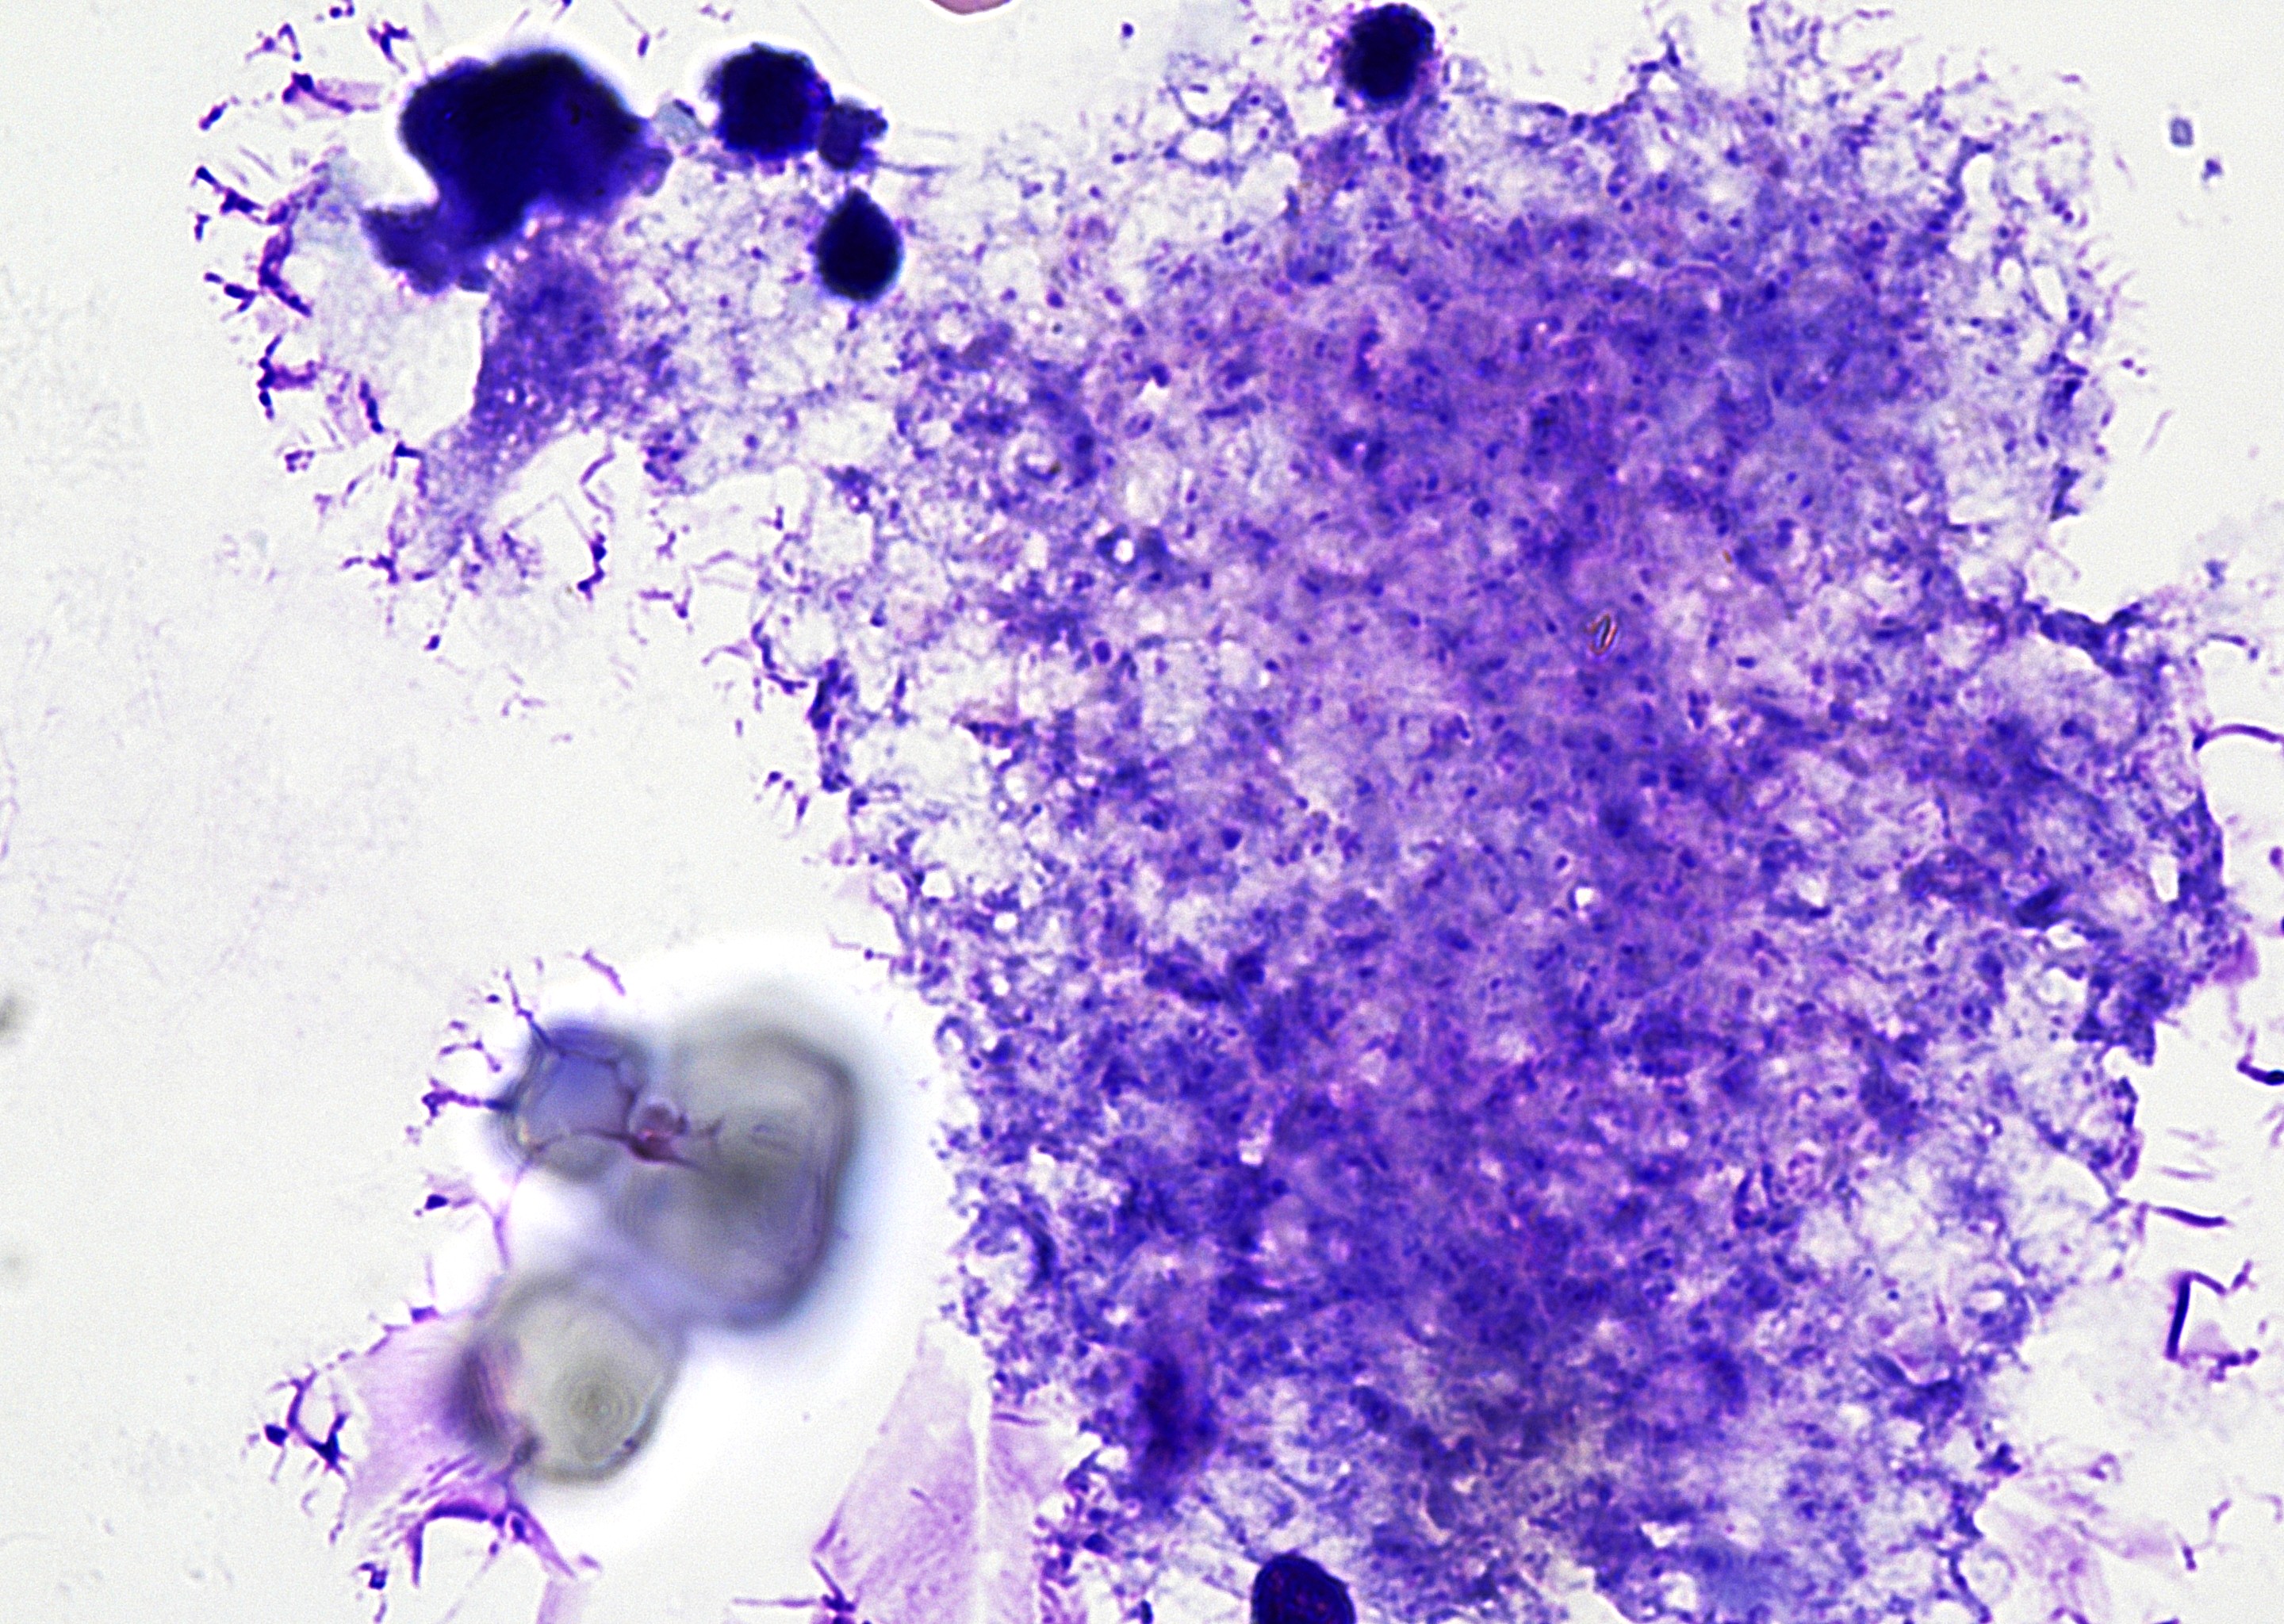 BAL with a colony of numerous round to oval…
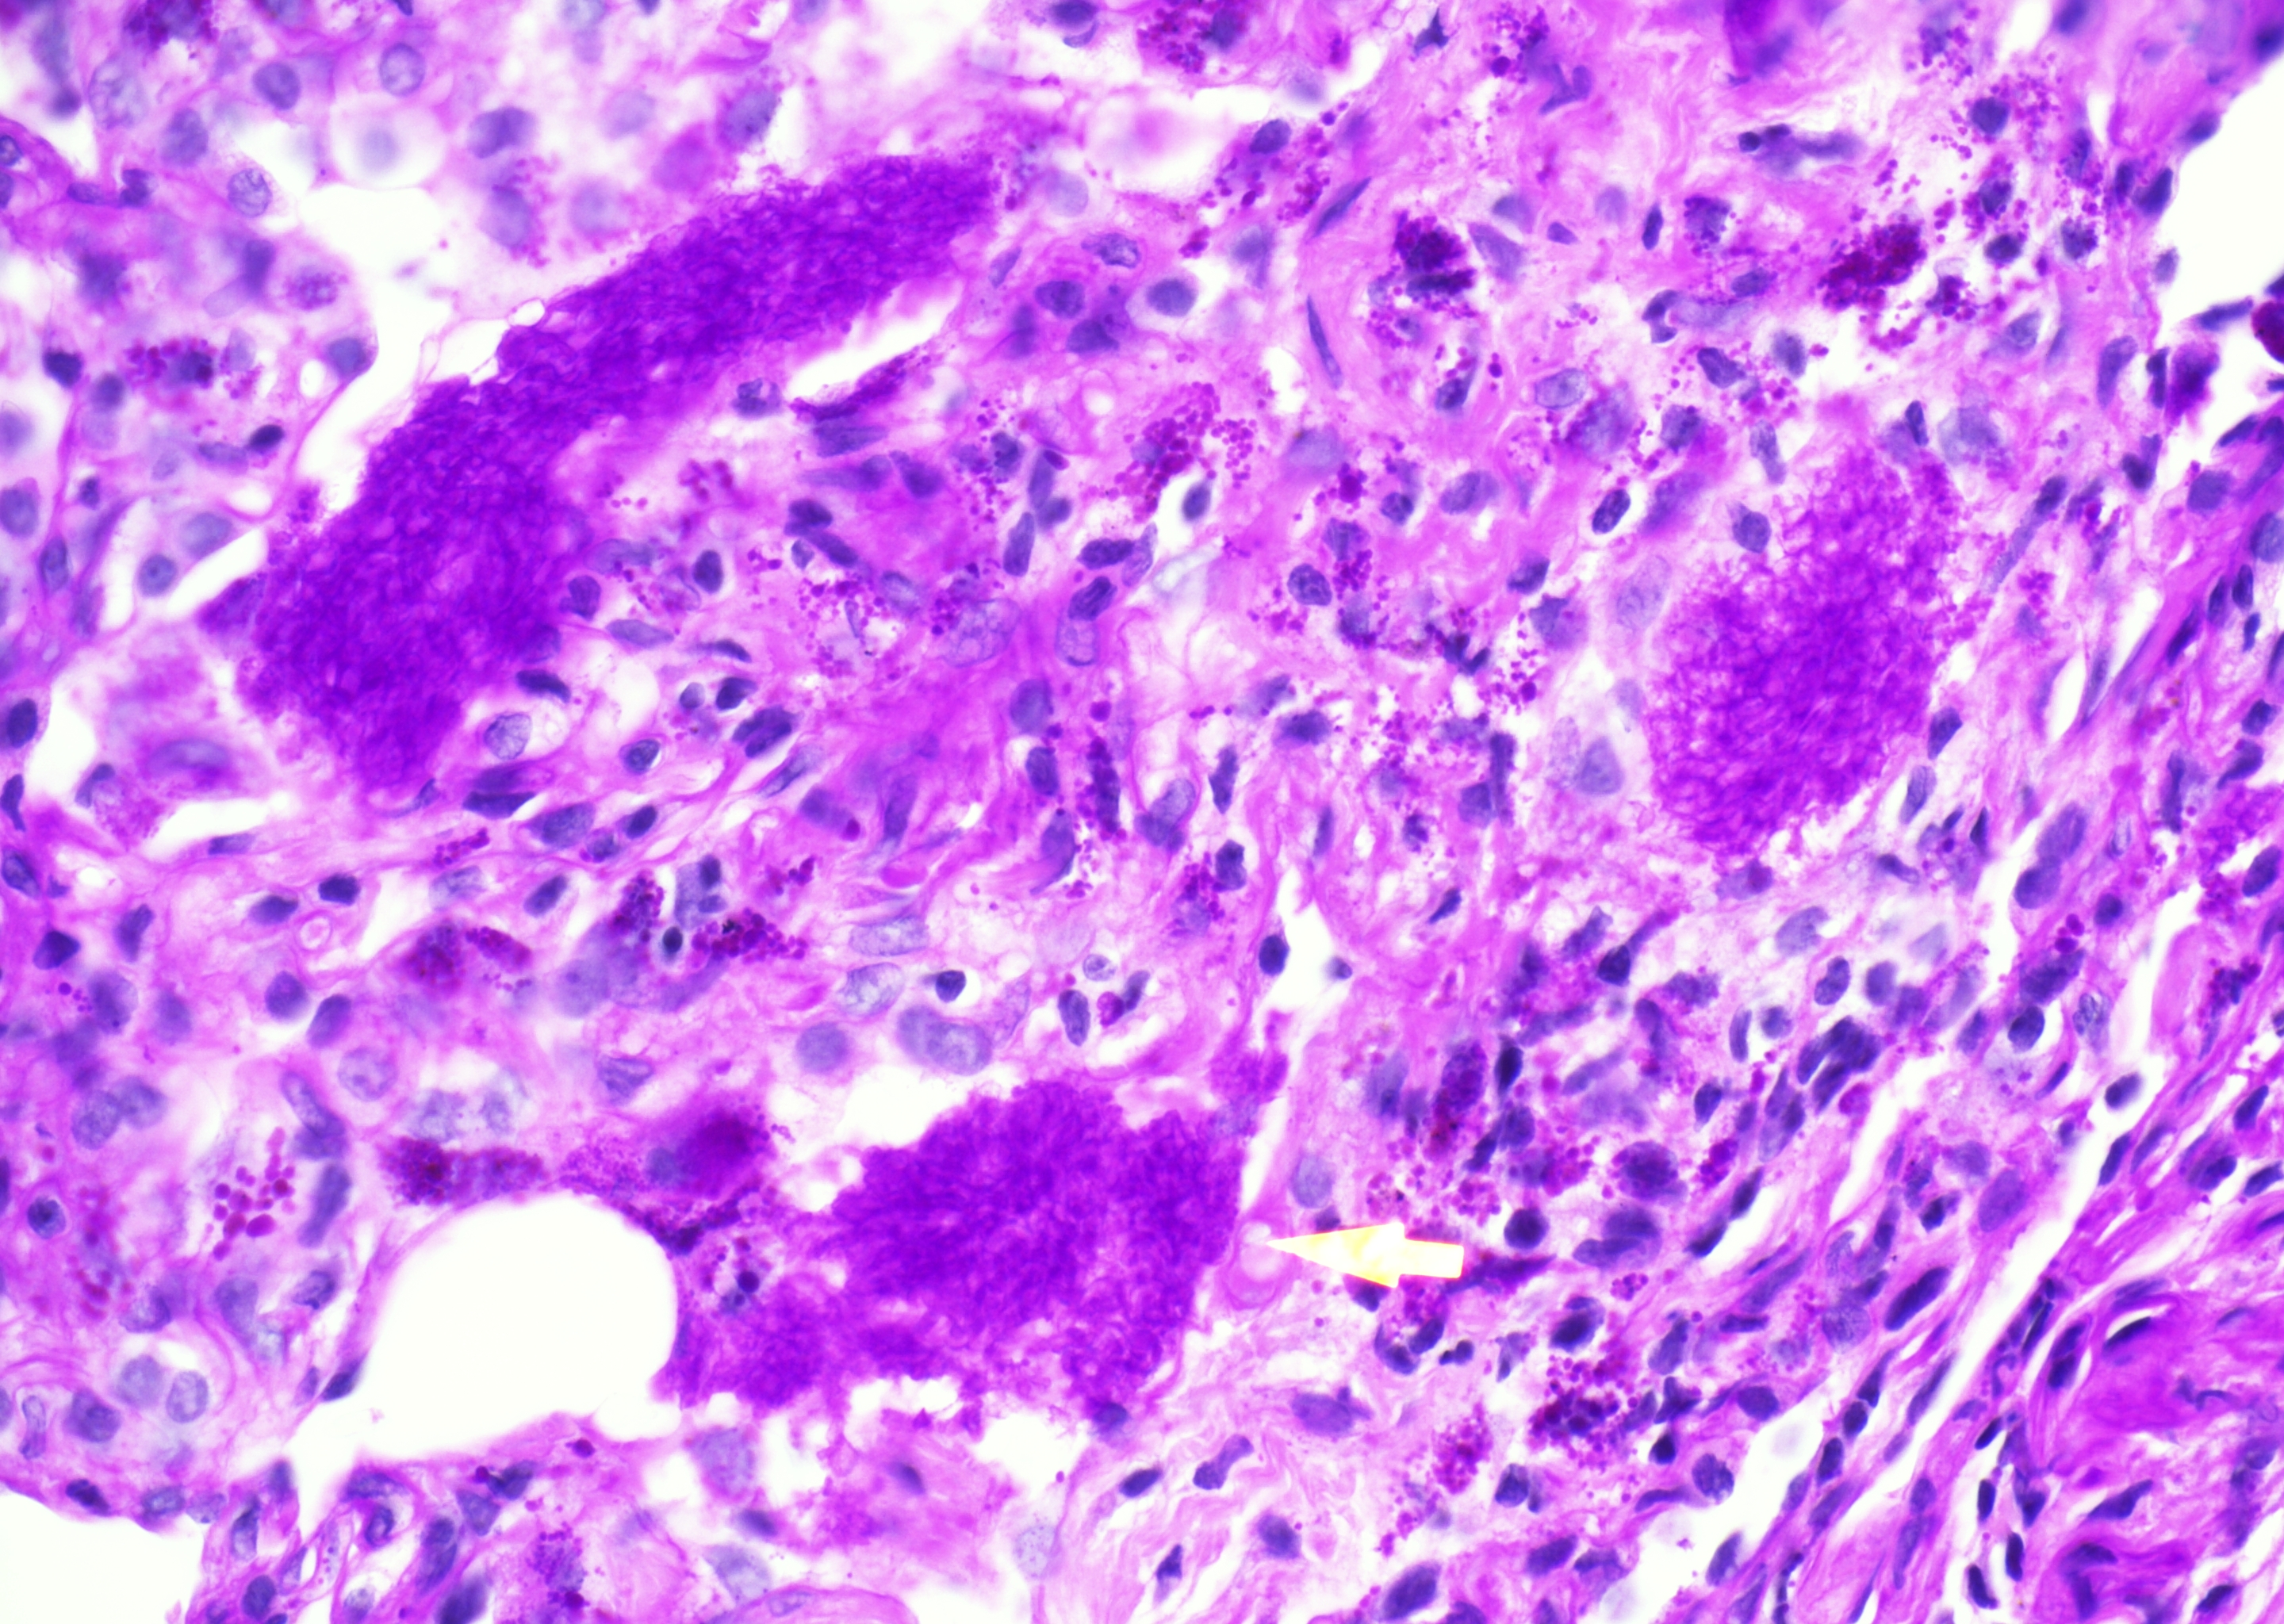 Lung biopsy with granular intra-alveolar…
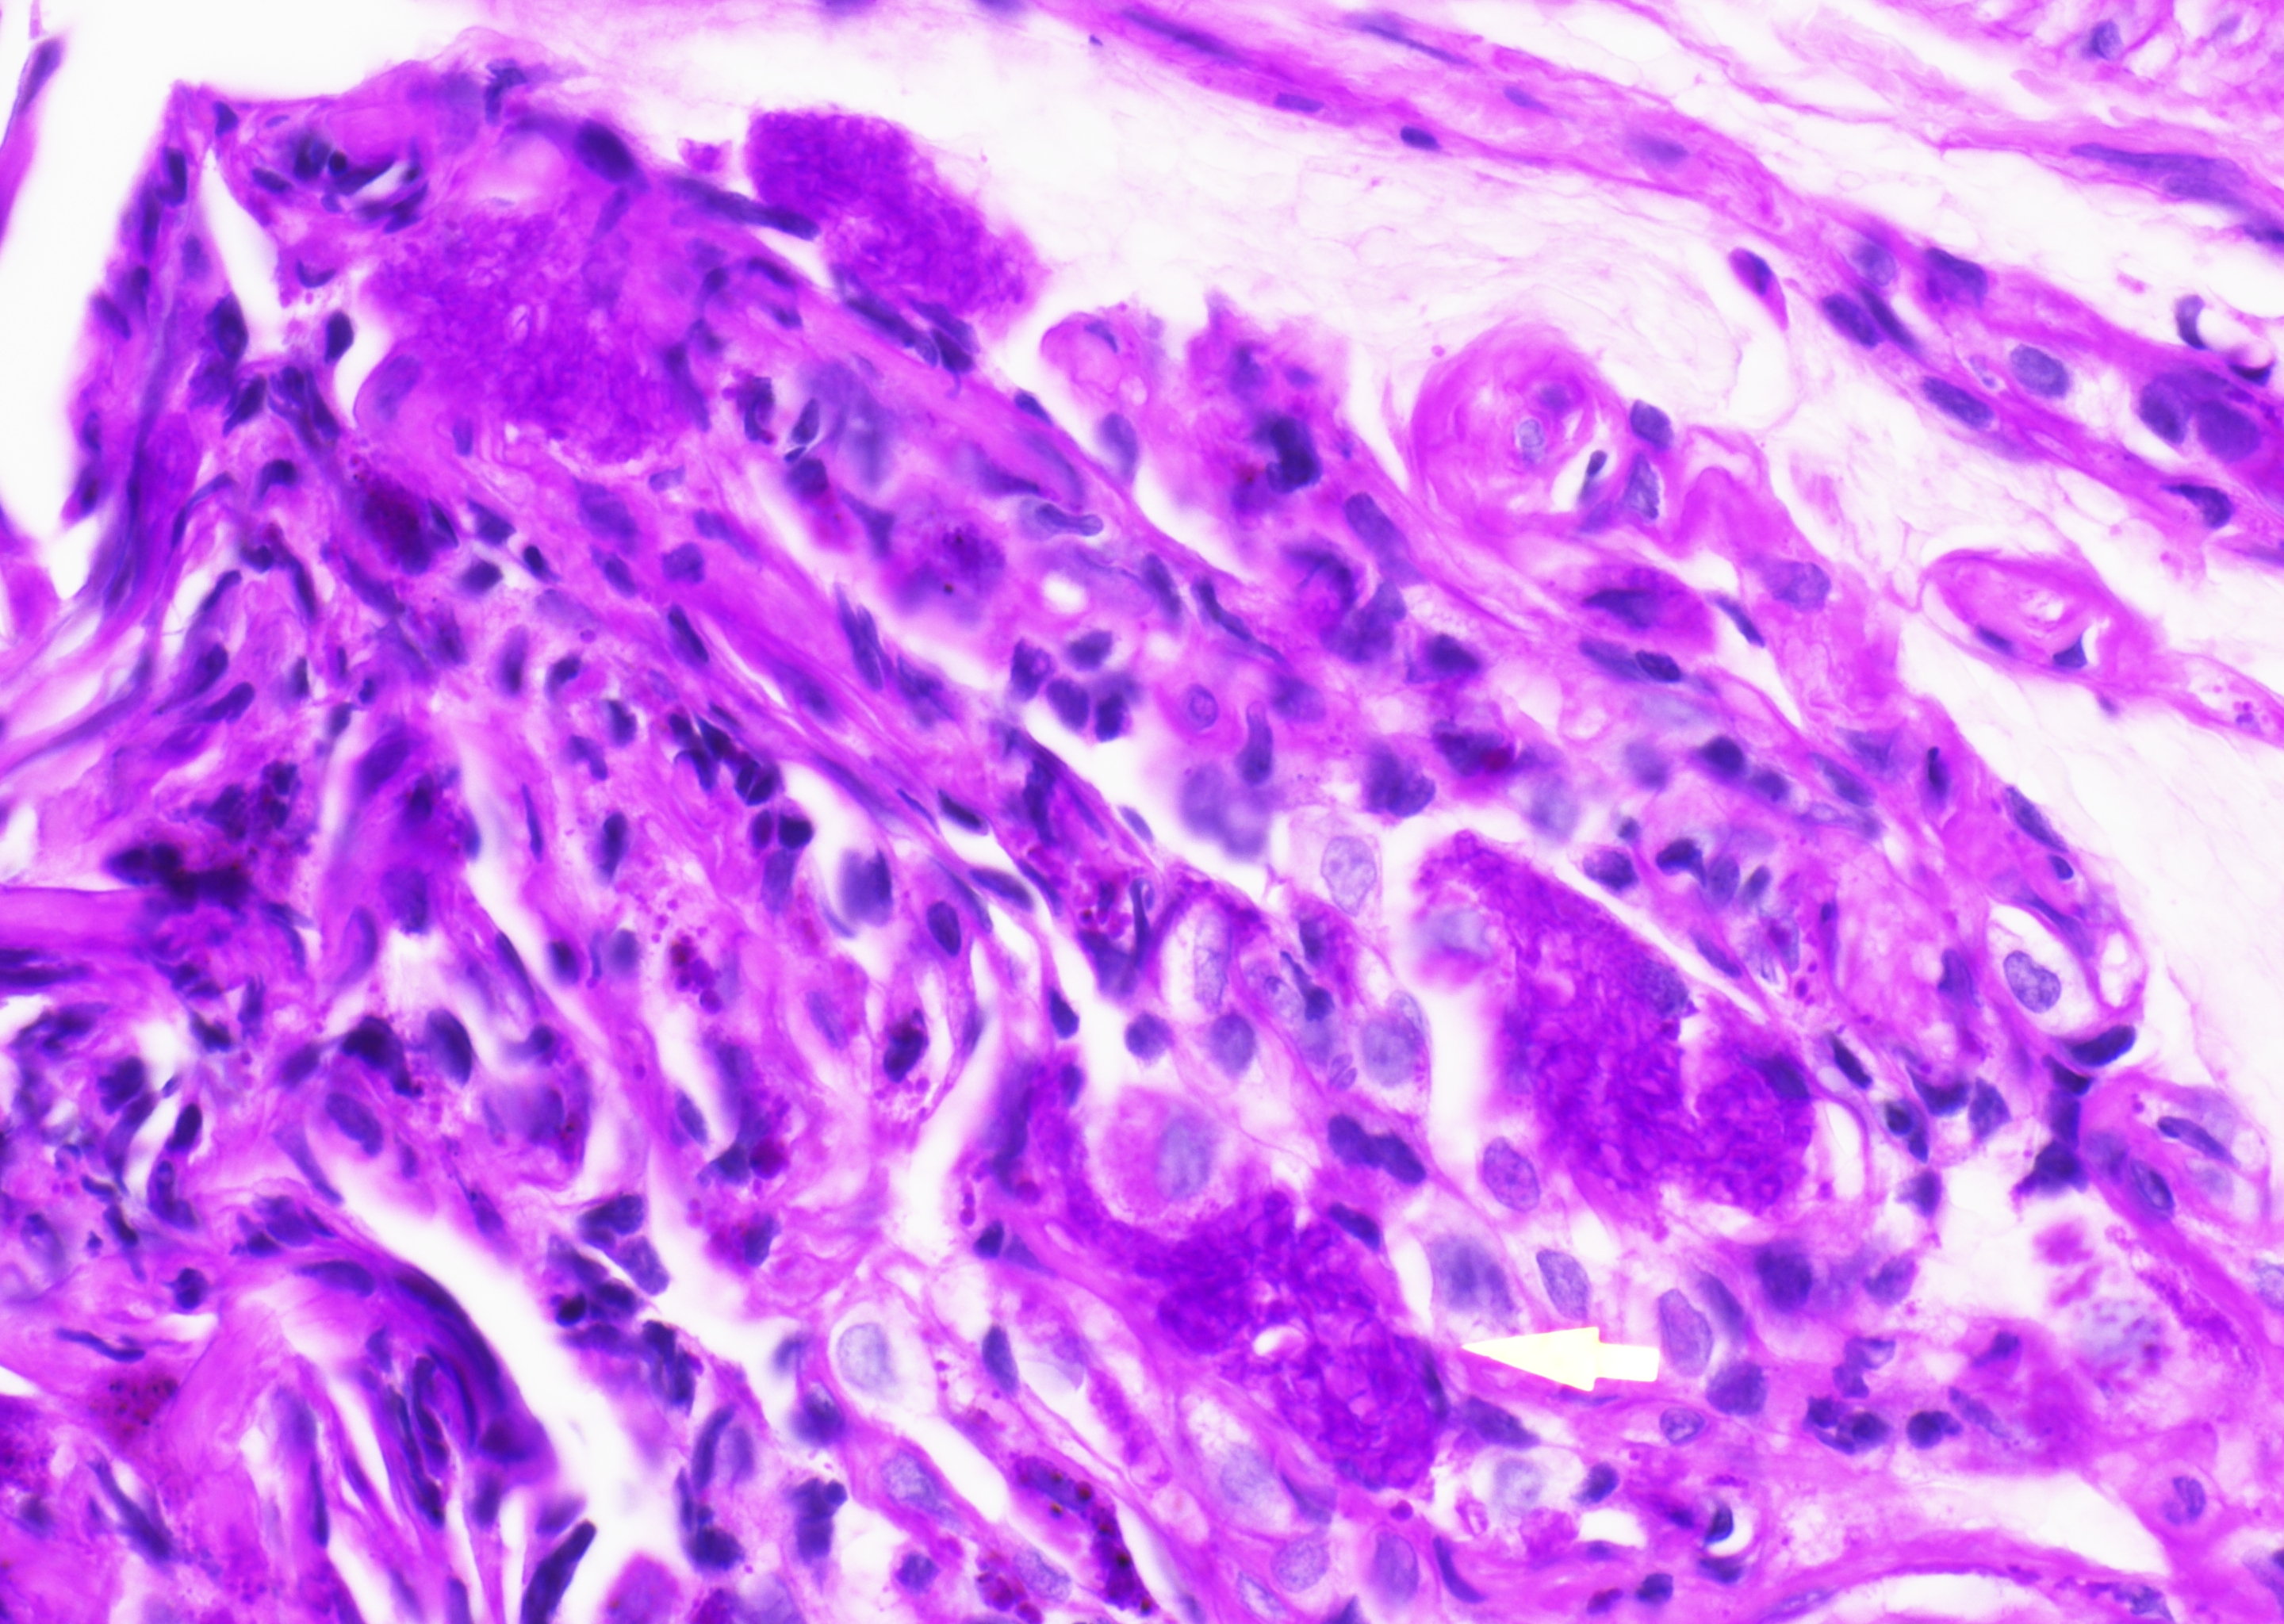 Lung biopsy with granular intra-alveolar…
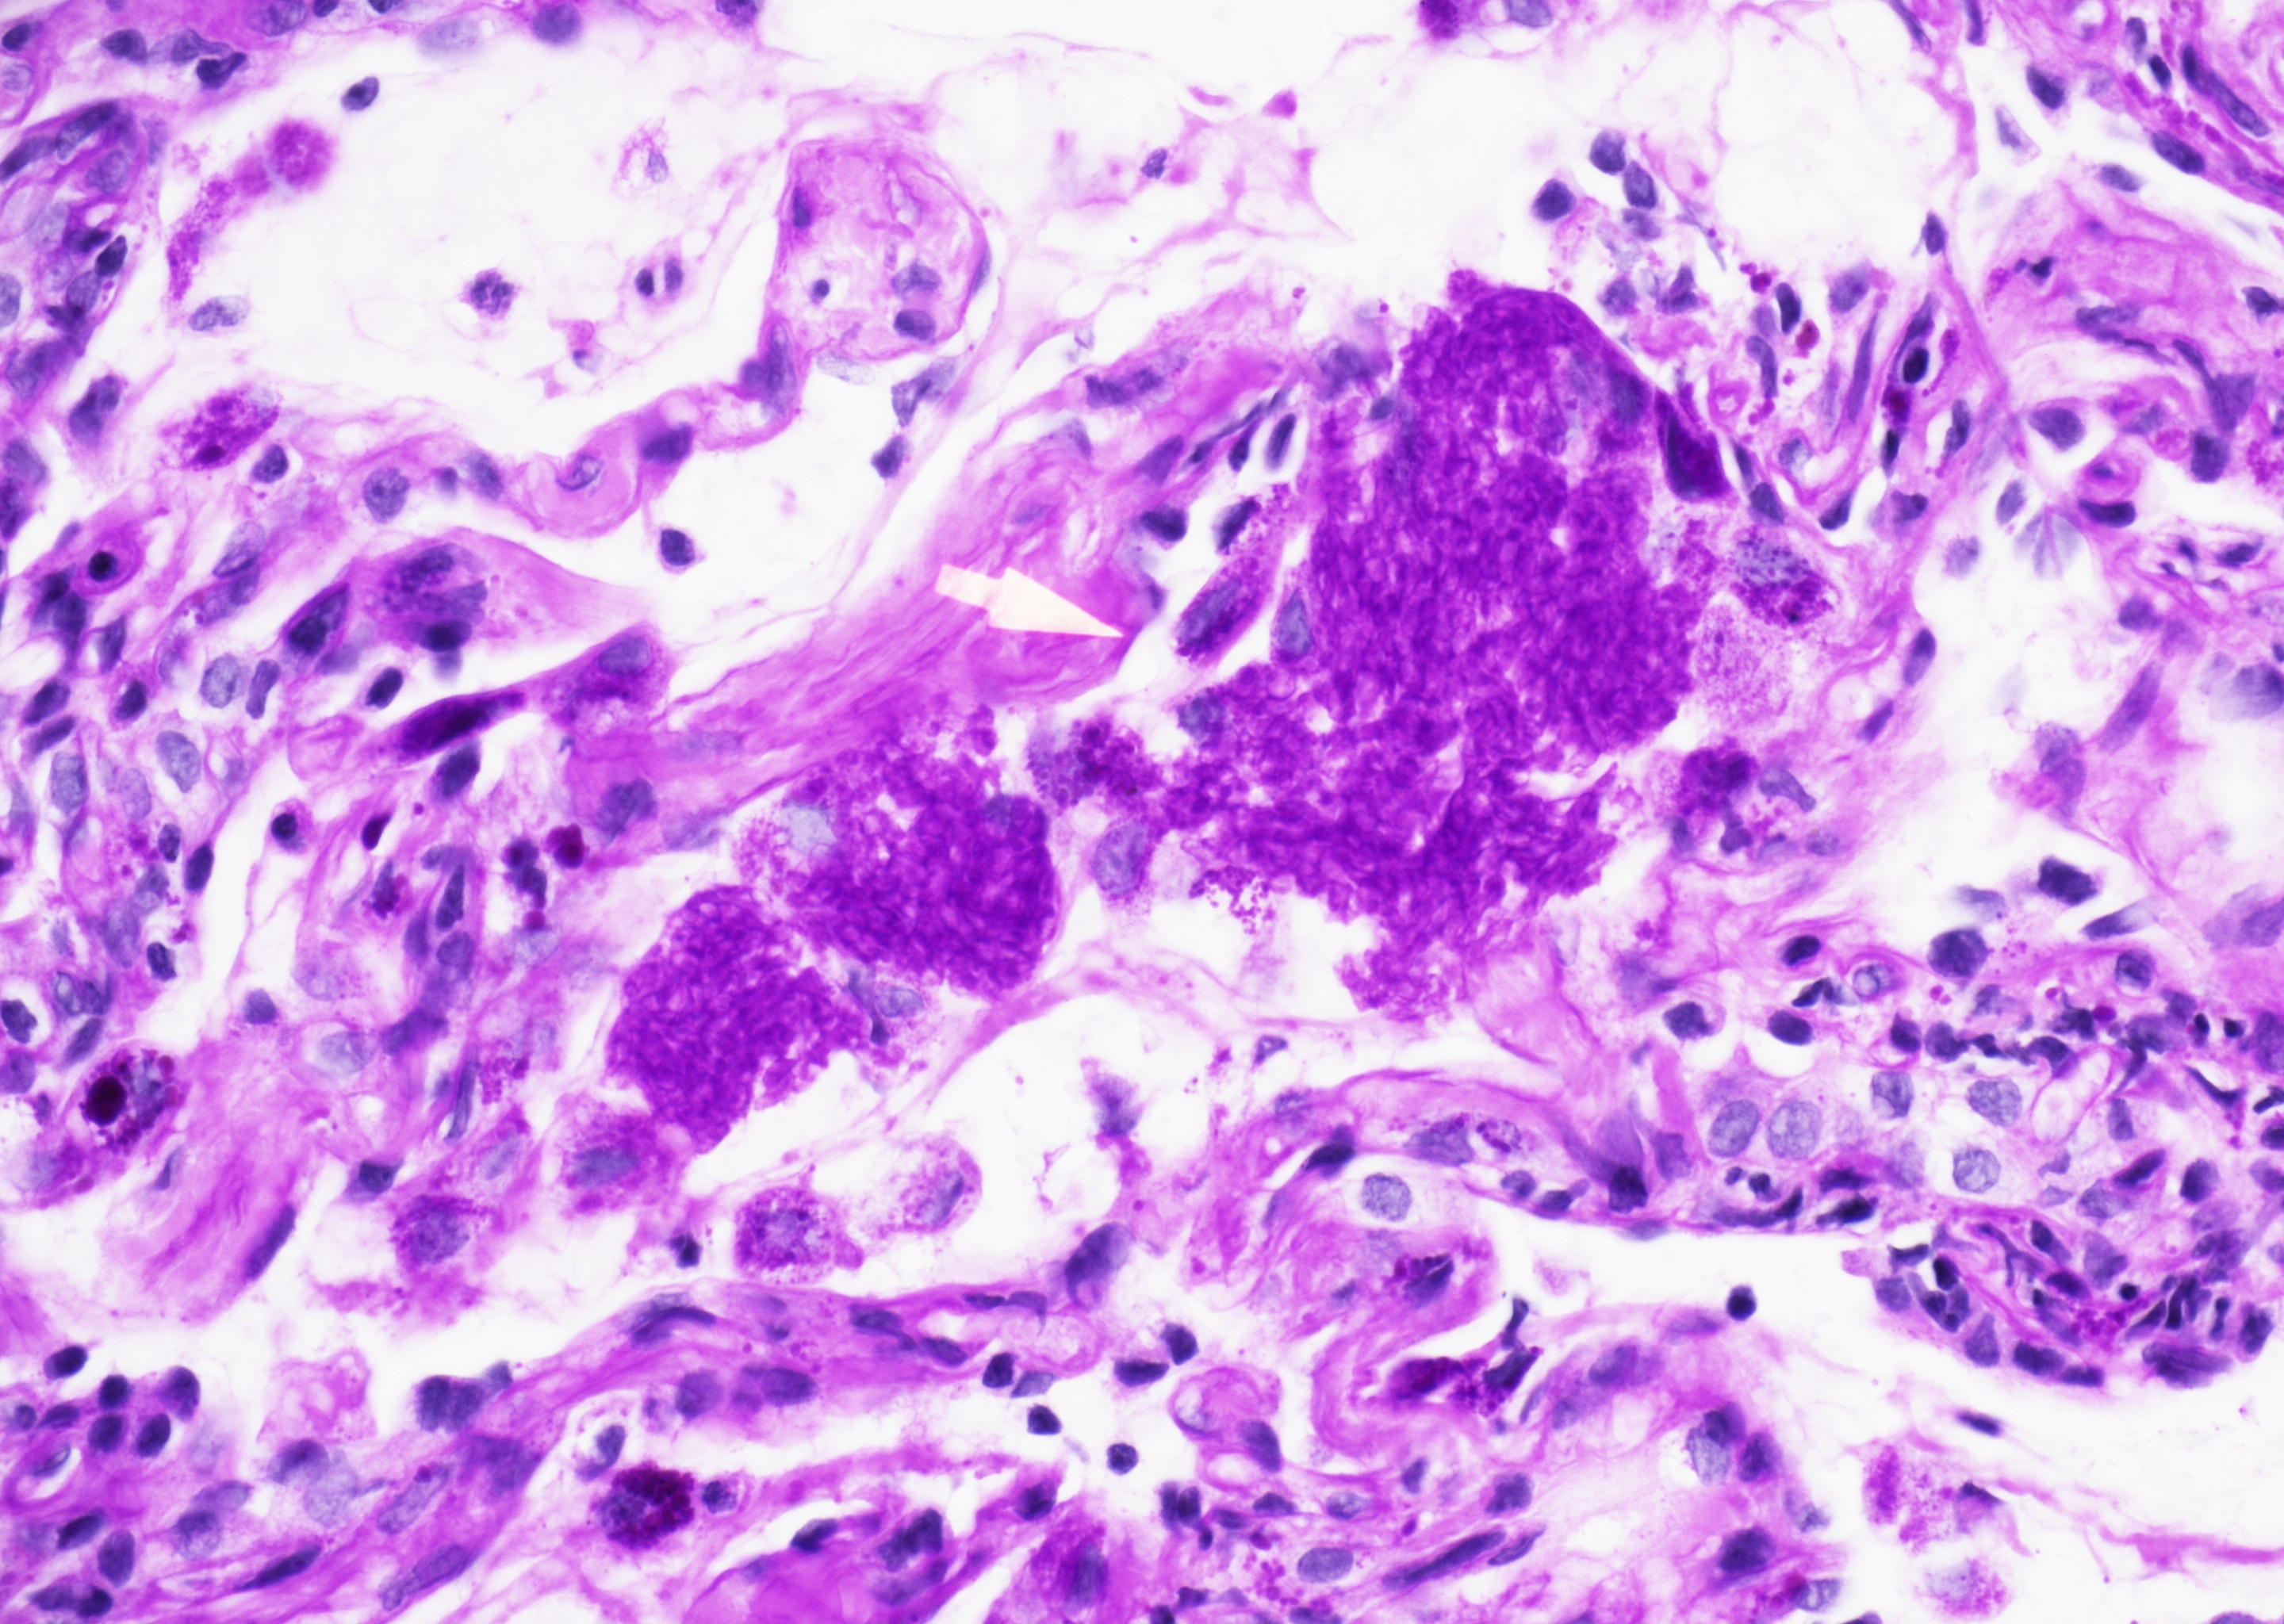 Lung biopsy with granular intra-alveolar…
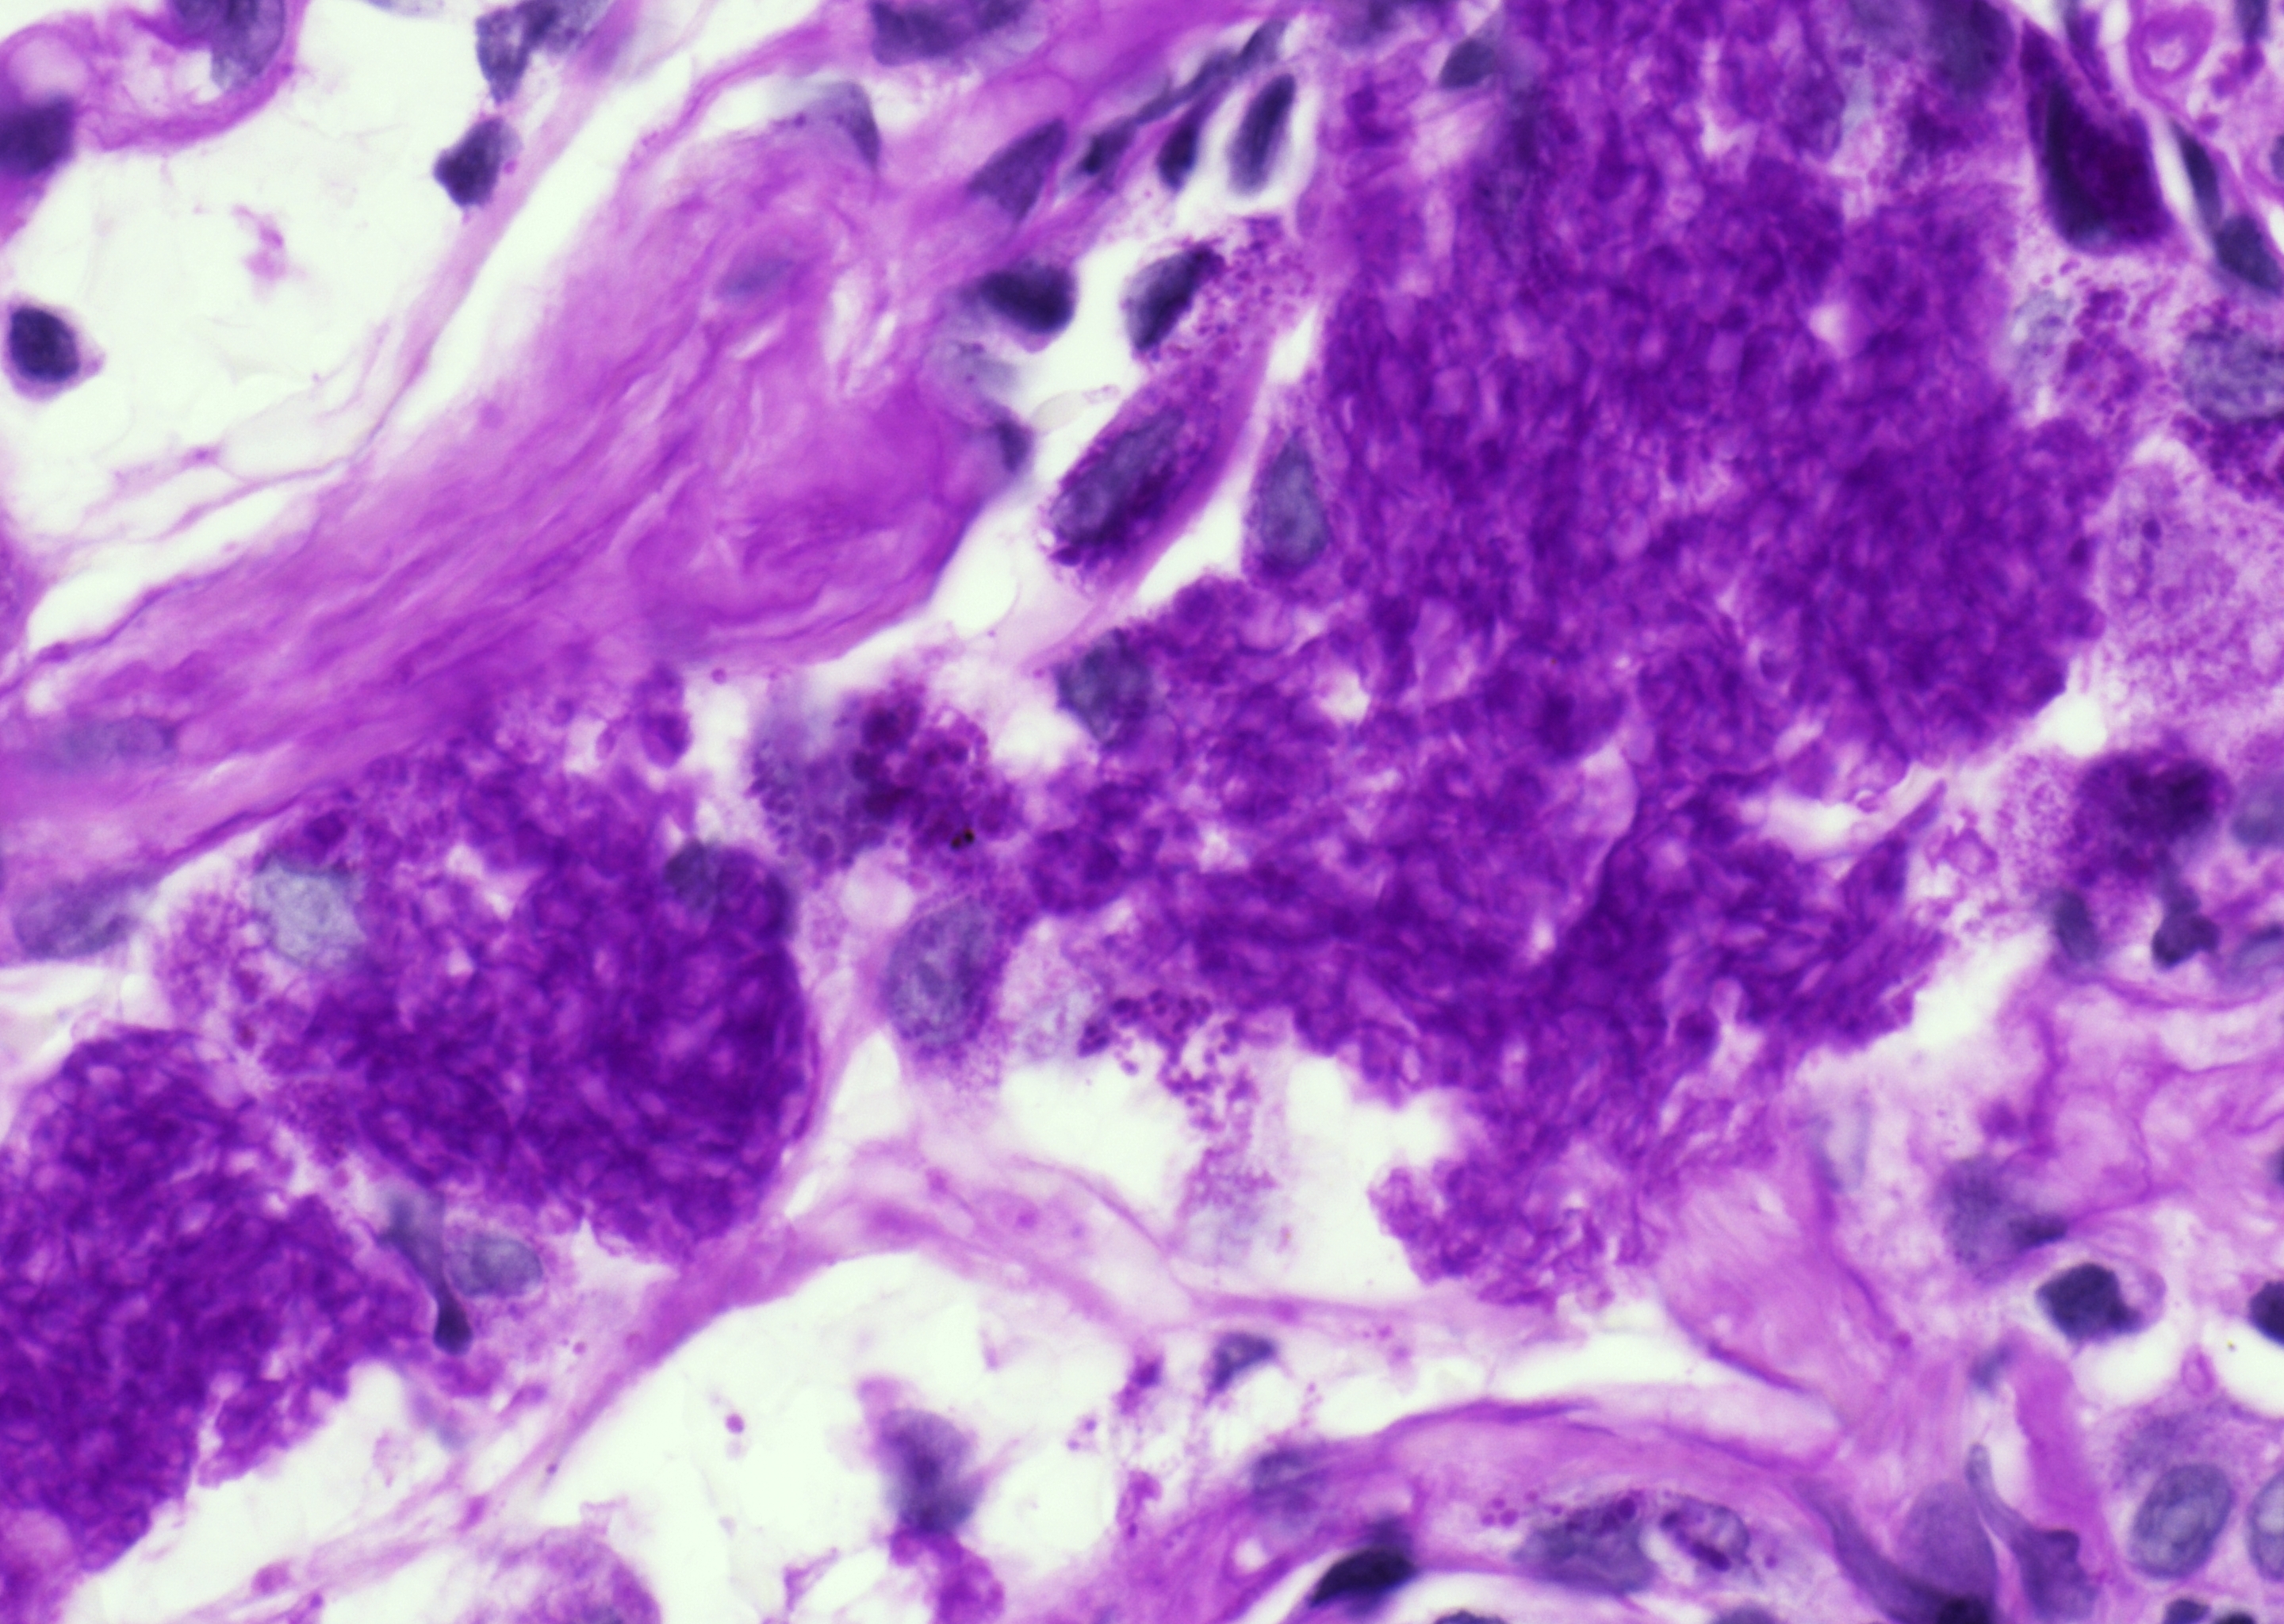 Lung biopsy, organism is being seen on a PAS…
 Lung biopsy, round to oval cysts with a…
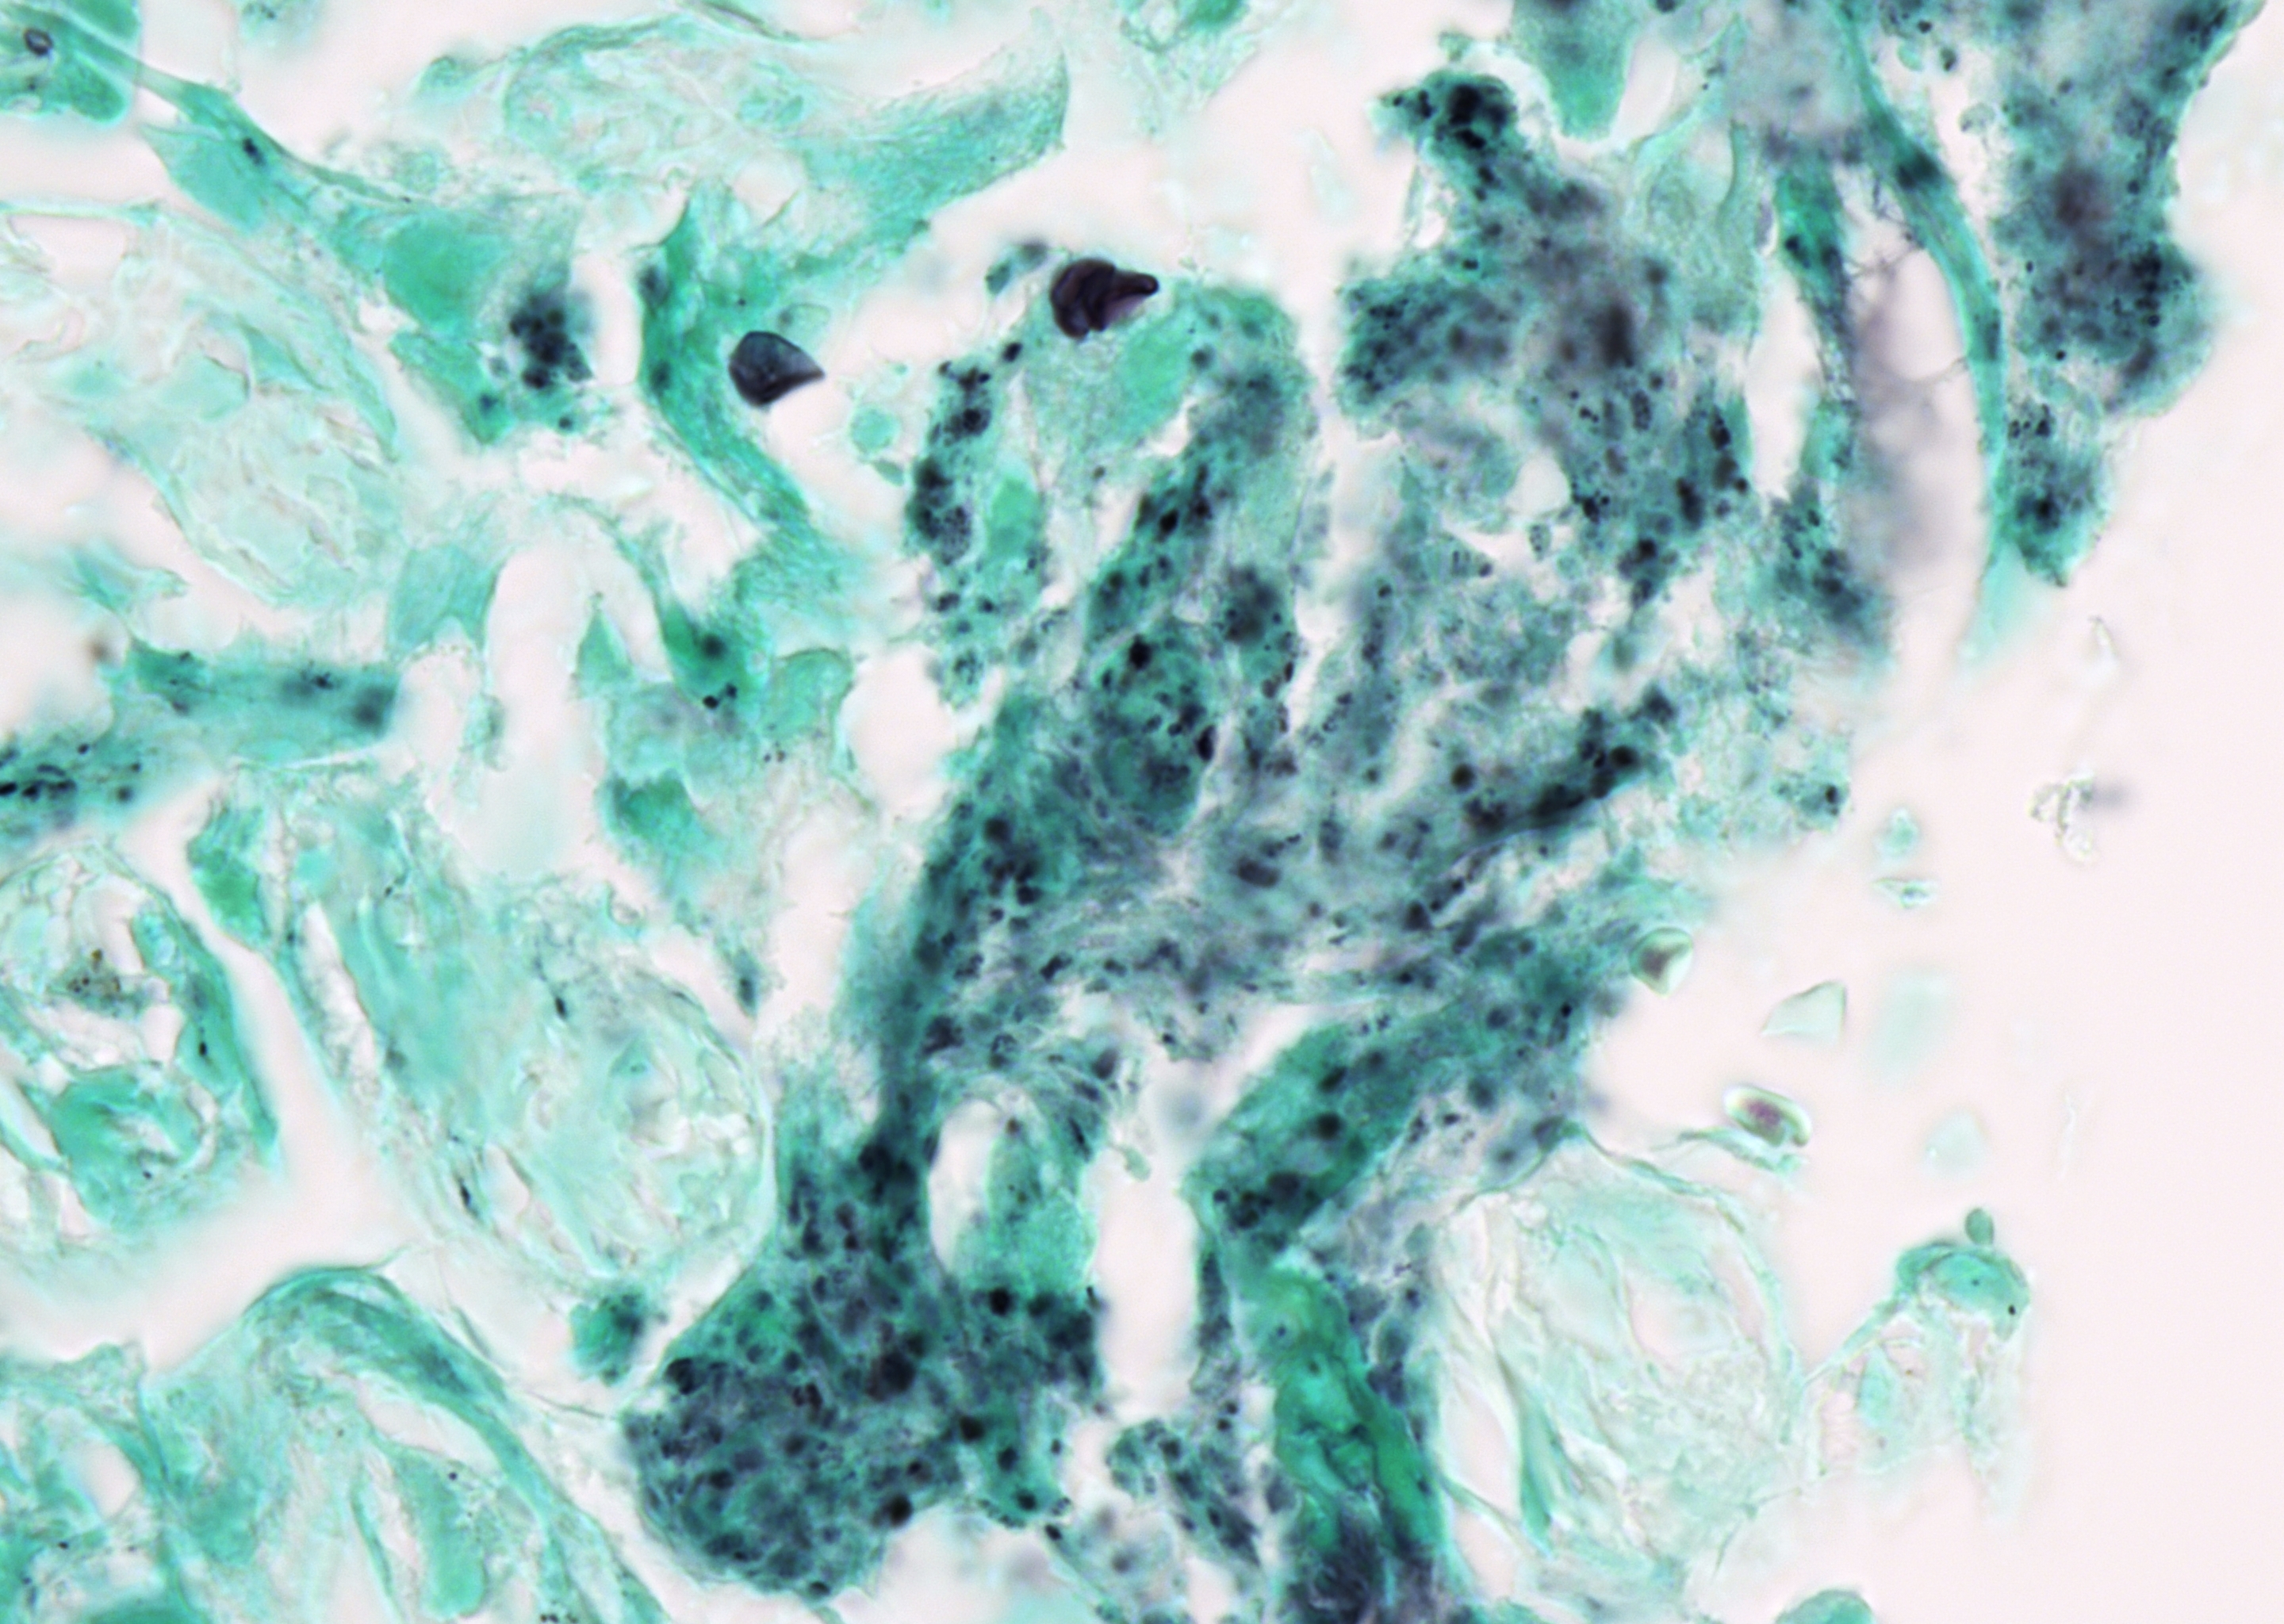 Lung biopsy, few cysts and numerous small…
Morphology
Cytology:
- BAL with overall normal cell distribution, with a possible increase in eosinophils and neutrophil granulocytes as well as lymphocytes.
- Background with alveolar macrophages and reactive alveolar epithelial cells, usually only few granulocytes, granulomas can be seen.
- Organisms in foamy alveolar casts
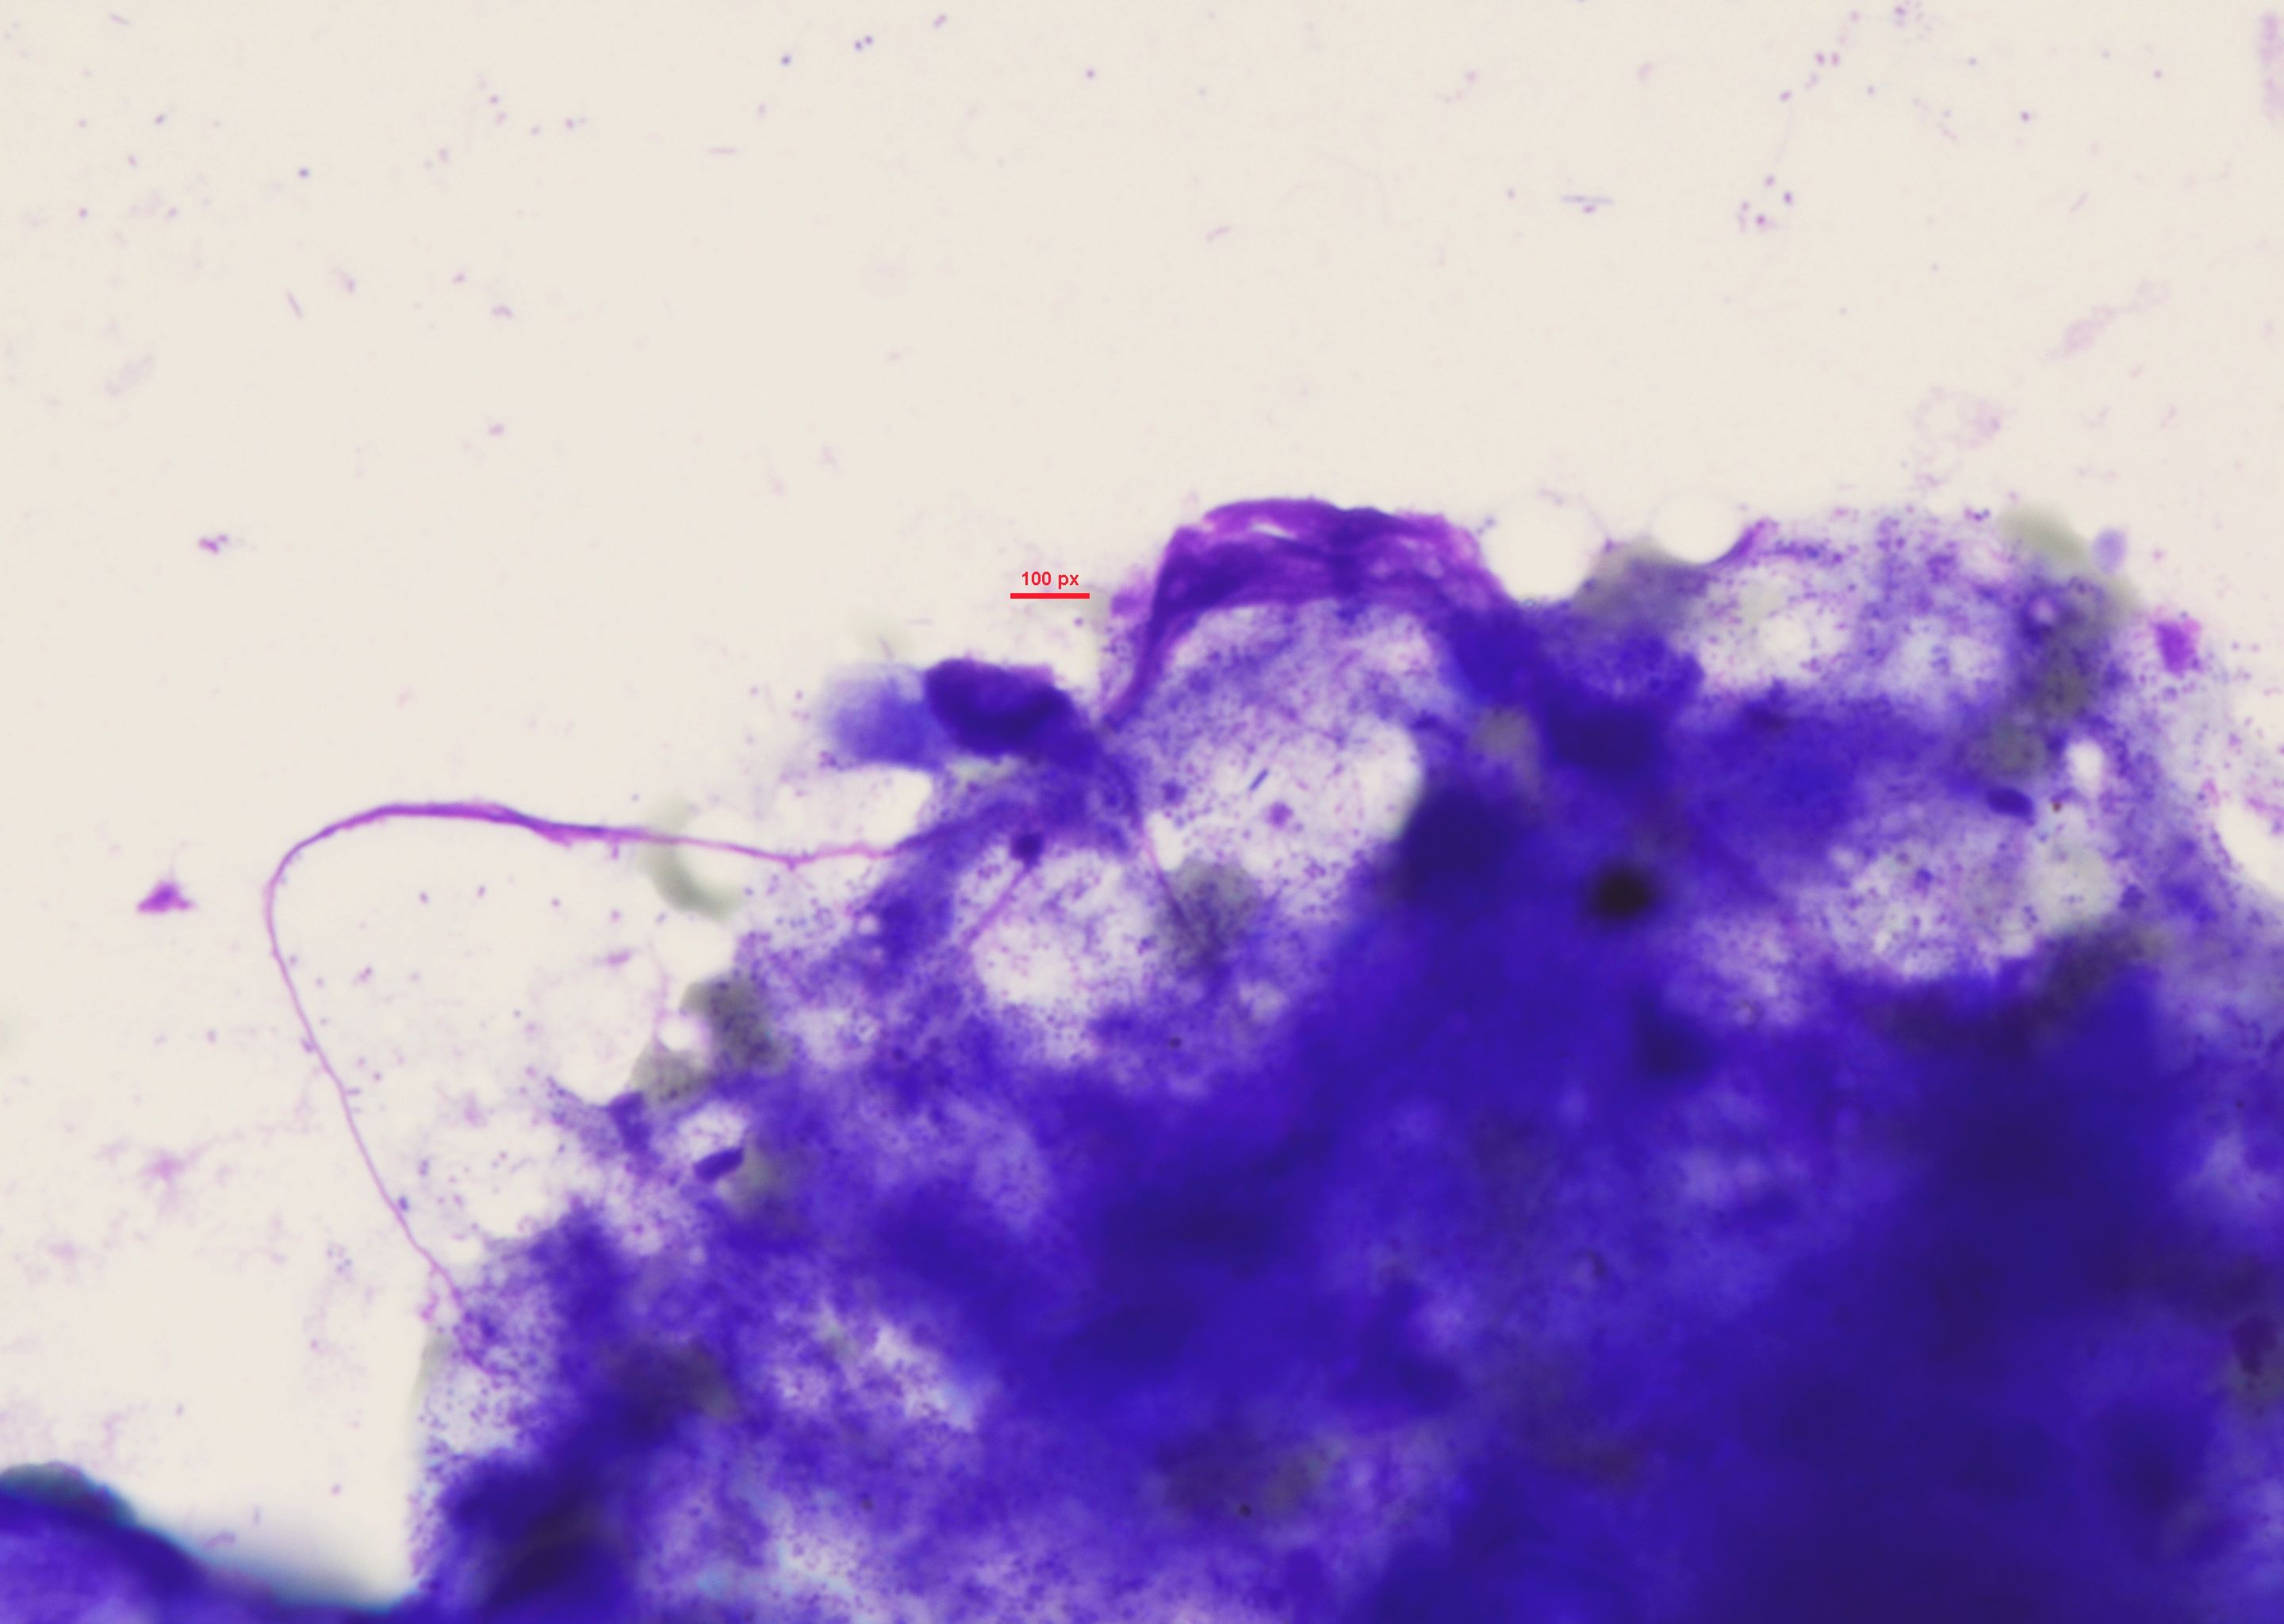
- Colonies consisting of numerous round to oval cysts (4–6 µm) containing multiple dot-like or short rod-shaped intracystic structures (sporozoites).
- No budding
- Occasionally, individual cysts within the cytoplasm of alveolar macrophages.
- Under Pneumocystis jirovecii (PJ) prophylaxis or therapy, clusters of sporozoites with a cloudy appearance may be seen, as the cyst wall is already destroyed.
Histology:
- The most characteristic histologic findings in lung infections include a prominent eosinophilic "foamy" intra-alveolar proteinaceous exudate containing numerous trophozoites, interstitial plasma cells, and reactive pneumocyte hyperplasia.
- Several unusual histologic patterns of Pneumocystis pneumonia (PCP) have been documented, for example, necrotizing granulomatous inflammation.
- Usually, even small foci of eosinophilic exudates with organisms are present across all patterns.
- GMS stain highlighting the typically spherical or crushed, boat- or helmet-shaped, non-budding cysts with prominent intracystic dots.
Special Stains:
- GMS highlights cyst walls.
- PAS is variable and generally less sensitive.
- On routine stains (HE, PAP), foamy intraalveolar exudate may be present, but organisms are often difficult to detect.
- Toluidine blue O and calcofluor white can also highlight cysts or cyst walls.
- Direct fluorescent antibody testing and immunohistochemistry increase sensitivity, especially when morphology is subtle.
Differential Diagnosis:
- C. glabrata
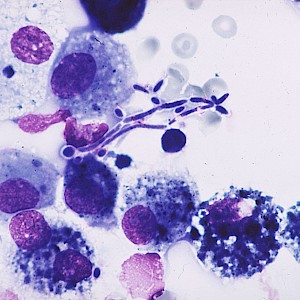
- Histoplasma spp.
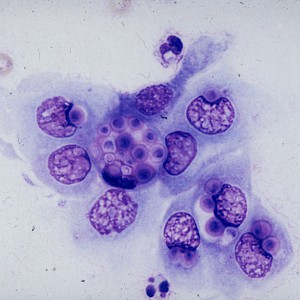
- Cryptococcus spp.
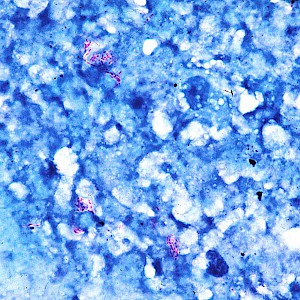
- Tuberculosis - necrotizing granulomatous inflammation with positive AFB
- Noninfectious causes/diseases
- Foamy alveolar casts can be mistaken for conditions such as pulmonary alveolar proteinosis, corpora amylacea, amyloidosis, or remnants of lysed red blood cells.
Clinical notes
Dry cough, dyspnea, and fever are the main symptoms of PCP. Radiologically, bilateral, diffuse reticulonodular infiltrates can be detected in over 90% of cases.
Ancillary Testing
PCR, Immunofluorescence (Sputum, BAL), Detection of beta-(1,3)-D-glucan (component in organims' cell wall) in serum or BAL fluid, IHCAdditional Information
PJ has asexual trophic and sexually reproductive cystic forms.
BAL is the material of choice to detect PJ. Induced sputum and bronchial secretions are significantly less reliable. Diff-Quik®, MGG, and PAP stains highlight both the cyst wall and the embedded sporozoites.
PJ is a ubiquitously occurring ascomycetous fungus. PCP is considered an opportunistic infection that occurs in immunocompromised patients. PCP is classified as an AIDS-defining illness and is often the first symptom in HIV-positive patients, particularly when the CD4⁺ T-helper cell count falls below 200 cells per microliter. In the late 1980s, the incidence of PCP among HIV-positive individuals ranged from 55 to 75%. In recent years, treatment and prophylaxis have led to a significant decline in PCP cases.
Primary transmission of PJ occurs via the airborne route. The first exposure commonly occurs during childhood. PJ colonizes the airways and is prevalent in the lungs of immunocompetent individuals. Symptomatic disease in immunodeficient patients is likely due to the acquisition of different PJ strains from other individuals (1). The pathogen almost exclusively causes PCP; clinically relevant infections in other locations are extremely rare.
Differential Diagnosis
References
- Skalski JH, Kottom TJ, Limper AH. Pathobiology of Pneumocystis pneumonia: life cycle, cell wall and cell signal transduction. FEMS Yeast Res. 2015;15(6):fov046. doi:10.1093/femsyr/fov046